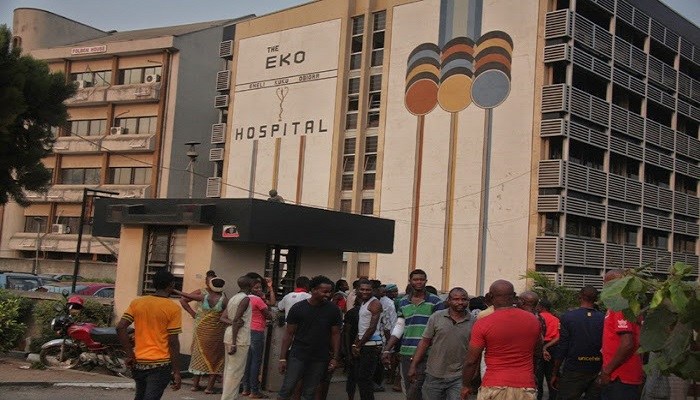The Senate has summoned Godwin Emiefele, Governor of the Central Bank of Nigeria (CBN); Kemi Adeosun, Minister of Finance; and Mansur Dan-Ali, Minister of Defence, to explain the “unlawful withdrawal” of $462 million from the Federation Account.
The summons resulted from a point of order raised by Sam Anyanwu, Chairman of the Senate Committee on Ethics and Privileges, who said the withdrawal was made without legislative approval as required by law.
To back up his motion, Anyawu referred to Section 80 (2) and (3) of the 1999 Constitution, which prohibits the withdrawing of money from the federation’s “consolidated revenue fund or an other public fund” without prior consent of the National Assembly or in the manner prescribed by it.
He submitted that the CBN Governor and the ministers of finance and defence should be summoned for appropriate questioning.
“Mr President, I have it on good authority that in March 2018, a whooping sum of $462 million was withdrawn from the federation account and paid for helicopters to an American firm called Helicopter Tecno Fights Helicopters and this was done without the approval of the Senate,” he said.
“As a citizen, senator of this place, I want to find out how this thing was done and I suggest that we invite the CBN governor, the Ministers of Finance and Defence to tell us how this money was withdrawn and paid to an American companu without the approval of the Senate.”
The Senate then referred the matter to the Committee on Appropriation to summon the trio and investigate the allegation. It also told the committee to submit its report to the house within a week.
This allegation is coming barely two weeks after President Buhari ‘approved’ the release of $1 billion from the Excess Crude Account (ECA) “for the purchase of more equipment for the military”.
Rochas Okorocha, Governor of Imo State, says he has no serious opposition going into the 2019 senatorial election, as he had retired the likes of Arthur Nzeribe and Achike Udenwa, who used to be political heavyweights in Imo State.
Okorocha expressed certainty that Uche Nosu, his son in-law, would win the governorship seat in Imo State, while he would himself clinch a seat in the Senate, after which he will succeed President Muhammadu Buhari in 2023.
“Nwosu will win in 2019,” he said on Tuesday while addressing some politicians who paid him a courtesy visit at the Government House in Owerri, the Imo State capital.
“Don’t be afraid, I am there. I have retired the Arthur Nzeribes, the Udenwas; now I will retire the rest of them finally.
“I know them and they know me; their plan is to push me so that they can get the Senate. It’s a lie; I will run for the Senate as well.
“Nwosu is the least of the political children I have trained but I don’t know any of them as much as I have known him. I took him up when he was just nobody and he grew to the height he is now, his only sin is that he is my son-in-law.”
Expressing delight at Buhari’s decision to seek reelection, Okorocha said: “Buhari will win again and again. After Buhari, the turn will come to South-east and it will be the turn of Okorocha.”
Festus Keyamo, Senior Advocate of Nigeria (SAN) has been appointed Director of Strategic Communications, for President Muhammadu Buhari’s 2019 reelection campaign.
Keyamo made this known via his verified Twitter handle on Tuesday.
“I will be making a formal statement on this much later,” he tweeted.
With this letter below👇, I have just been appointed the Director, Strategic Communications (Official Spokesperson) for the President’s 2019 Presidential Campaigns. I will be making a formal statement on this much later. pic.twitter.com/VxRZcI9Jdo
Keyamo, 48, hails from Ugheli, Delta State, and graduated from Ambrose Ali University, Ekpoma Edo State in 1992. He was called to the Nigerian Bar in 1993 and was elevated to the rank of a senior advocate in 2017.
In his capacity as spokesman for the Buhari reelection, he is expected to ensure that his principal wins the APC presidential ticket and, subsequently, the general election in 2019.
President Muhammadu Buhari apparently considers the huge cut to rice importation from Thailand one of his administration’s greatest achievements. During his ongoing visit to London, he has boasted to Justin Welby, Archbishop of Canterbury, and British Prime Minister Theresa May about Nigeria’s ‘road to food self-sufficiency’.
HIS CLAIMS
According to statements released on Wednesday and on Monday by Femi Adesina, Buhari narrated to the two personalities ― in what appeared almost like memorised speech ― how Nigeria has cut rice importation by 90 percent.
“I am very pleased with the successes in agriculture,” he told Prime Minister May, on Monday. “We have cut rice importation by about 90%, made lots of savings of foreign exchange, and generated employment. People had rushed to the cities to get oil money, at the expense of farming. But luckily, they are now going back to the farms. Even professionals are going back to the land. We are making steady progress on the road to food security.”
This claim by the President is backed by figures released by the Thai Rice Exporters Association, which detail rice exports from Thailand to all countries, including Nigeria, from 2015 to 2017.
In 2015, the Asian country exported 644,131 metric tons (MT) of parboiled rice to Nigeria. In 2016, this figure dropped drastically to 58,260MT. And, in 2017, it fell even more to 23,192MT, resulting in a 96.7% decrease in just two years. This is apparently great news for the country ― except that these figures do not tell the whole story.
FACTS AND FIGURES
Benin Republic has always been another major importer of rice from Thailand. In 2015, Thailand exported 805,765MT of parboiled rice to the West African country. This figure, however, skyrocketed to 1,427,098 in 2016, and 1,811,164 in the year that followed. The same trend can also be noticed regarding Cameroon, another country bordering Nigeria. It imported 449,297MT of rice in 2015, 505,254MT in 2016, and 744,508MT in 2017.
“Nigerians, of course,” Mohammed had himself confessed. “In fact, as Nigeria’s rice import falls, Benin’s rice imports increase. Most of the parboiled rice imported by Benin eventually land in Nigeria through smuggling.”
Even Audu Ogbeh, Nigeria’s Minister of Agriculture and Rural Development, admitted in 2016 that Benin traders imported parboiled rice shipped in from Thailand, “station themselves at our borders and smuggle these items into our economy”.
According to data from the International Grains Council, over half of Nigeria’s imports in 2015 entered from neighbouring Benin, where the duty on rice is only 12%, and most of Benin’s rice imports, up to 30,000 truckloads per year, are routed via transit shipments through Niger to the northwest of Nigeria.
It is also suggested that since Nigeria is the only West African country that exclusively consumes parboiled rice, it is easy to deduce that the 85% share of Benin imports that are parboiled are Nigeria-bound through the orchestrations of clever traders.
THEREFORE…
President Muhammadu Buhari has, therefore, been economic with the truth in his conversations with his English friends. Under his administration, Nigeria may have cut lawful rice importation by more than 90% but unlawful importation is still booming, which clearly means suggestions the country has equally made 90% progress on the path towards agricultural self-sufficiency are completely false!
EDITOR’S NOTE: All the names of cancer patients in the undercover parts of this story have been concealed as a mark of honour for their struggles and respect for their privacy. An undercover method was unavoidable, as it was the only way to ascertain the true quality of healthcare available to them in federal hospitals. The ICIR is in possession of video and audio evidence of ALL the findings of this story.
For a futile month in 2017 and two fruitful ones in 2018, ‘FISAYO SOYOMBO, Editor of the ICIR, was accompanied by a private oncologist in going undercover at two leading teaching hospitals in the country to ascertain the true quality of healthcare available to cancer patients. Together, they discover how the lack of functioning radiotherapy machines is impeding the treatment of numerous cancer patients and aiding the spread of the disease from a point in their bodies to others, leaving many of them stranded midway through their treatment and their families resorting to lobbying hospital officials. This is also a celebration of love — how cancer patients are fighting to see every new day by merely seeking to repay the care and faith and sacrifice of their lovers.
This is one of the most intense, riveting love stories you will ever read. Contrary to what you may be thinking already, it isn’t set in the Hotel President Wilson in Geneva, Switzerland — the world’s most expensive hotel — or in the famous Burj Al Arab in Dubai, the third tallest and fourth largest hotel in the world. It isn’t set in Paris, the fabled ‘city of love and romance’, either. Instead, this true life story is set in the frenetic city of Lagos, specifically domiciled at the gynecology ward of the Lagos University Teaching hospital (LUTH). Dateline, February 2018.
A dark, beautiful young lady from Edo State — confined to the bed by terminal sickness — writhes in agony. She twitches her right fingers but the rest of the arm is static; it’s swollen and bandaged, the source of enormous pain. She closes her eyes and grits her teeth as though mustering all the strength within her in an attempt to say something to the doctor, but she doesn’t. Weak and helpless, she gives up.
Her boyfriend — a dark, handsome, confident young man from Delta State — cut a forlorn picture. The agony in his eyes is palpable; it is clear he wants to help, but he can’t. He can’t even hold her hands in his; one touch and she’d scream in excruciating pains. Instead, he stares at her in consolation, wearing a sombre look suggesting he would rather bear the pains on her behalf.
THE POWER OF LOVE
One of his girlfriend’s breasts has been cut off; mastectomy is what the doctors call it. It is from there that the cancer raging through her body emanated. In all, she has undergone surgery, chemotherapy, radiotherapy — the three commonest medical solutions to cancer — yet her condition is deteriorating. She is becoming paler, losing weight, now unable to move — because the cancer has so spread round her body that she now suffers from metastatic neuro disease. Also, due to the cancer, she has lymphedema, responsible for the swelling of her eyes and right arm. She has intense chest pains and struggles for breath after weeing. She’s on oxygen as well. And what more? Breasts don’t regenerate; that breast is gone forever. Still, he loves her.
“I love her so much. She was my crush then when we were in Uniben but she used to play hard to get,” he says. “I never knew we would meet again in Lagos.” For the first time in a pain-laden 15 minutes, she blushes, her face lightening up and her lips slowly parting to release such glorious smiles that set one wondering just how pretty she must have been in her healthier days. Love, oh love! Such medicine even to the sick.
They have been dating for roughly six months. After losing track of each other back in Benin, where they both grew up, they met fortuitously on the streets of Lagos in January 2017. She had just undergone surgery at the time; and as the friendship blossomed, she told him she had cancer, and that one of her breasts had been removed.
“Trust me, it wasn’t an issue,” he says of the breast removal. “Even she was shocked [by my reaction] when she told me; I never felt anyway. If you love someone you have to accept them the way they are; it’s the truth. Life goes on. You can’t hold on to that, because it’s not her fault that she has cancer. I have accepted it.”
What he has accepted is often not so easy to deal with. As explained by the external oncologist who joined the journalist in entering the hospital undercover, there are ample examples of husbands who divorced their wives after mastectomy, despite already having kids after several years of marriage. In fact, there are cases of husbands who prevented their wives from undergoing the procedure, despite knowing that retaining the breasts literally meant a death sentence.
One more time she clenches her fists in pain and her man’s face contours into a frown. It’s such an unpleasant sight to behold. For how long will they endure this pain? When will she be strong enough to get out of the hospital and return to her normal life?
“I pity her a lot,” says the undercover doctor. “But I pity her boyfriend more. This lady I see has one year — probably two more — to live. The doctors handling her case must have told her, and I hope she has told her man — because no doctor will. The doctor tells the patient the truth but no one else. There is a doctor-patient confidentiality that forbids the doctor from opening up to anyone else other than the patient.”
BLAME CANCER, BUT BLAME THE HEALTH SYSTEM MORE!
When — or if — she dies, her death will be blamed on cancer, but make no mistake: the Nigerian health system would have been hugely complicit. Her death would have been fast-tracked by the many inadequacies of a comatose public health system. Why?
Last year, she was scheduled to undergo external beam radiotherapy (RT) treatment, ideally delivered by a machine called Linear Accelerator, or Linac for short. All linacs generate high energy x-rays (photons), which are then carefully aimed at the area of the patient’s body being treated by the Consultant Oncologist. First, LUTH’s RT machine is not linac, therefore incapable of producing the maximum result. Two, she was scheduled for 18 courses. But after 10 rounds, the RT machine broke down (in June 2017). Thus marked the end of her radiotherapy treatment — just at the halfway mark. Almost one year on, the machine hasn’t been fixed, neither has a new one been bought.
In any case, there is good reason to doubt the efficacy of those 10 sessions, as she recalls the difficulties faced by patients in the final days of the broken-down machine. “There were serious issues with the machine,” she says. “A lot of people were having complications; some were overdosed, others under-dosed.”
A LETHAL PAUSE
According to the undercover oncologist, the aborted procedure she was undergoing is called ‘adjuvant radiotherapy’, that is radiotherapy done following a debulking surgery (also known as tumor removal surgery).
“The courses are spread out in such a way as to target the remnant metastatic tumour cells,” he explains. “She was placed on 18 courses of radio, spread out over months, in order to deal with the problem cell by cell. So, what happened when the radiotherapy machine spoilt is that you stopped the process of clearing the metastatic cells.”
The implication is that those cells that had not been cleared after the 10 courses would continue giving her symptoms manifesting as pains in parts of the body. “Cancer cells feed on blood, so the person will still look sickly,” he says. That is the best scenario for the luckiest patient.
“But the worst — which is usually the case and which has clearly happened in this case — is that the metastasis continues, which means as the cells around her breasts were being targeted, the metastasis could have gone to the lungs and could have even gone as far as the brain — because the process of spread is through the blood or through the lymph nodes,” he adds. “The patient can start coughing blood because the cancer has gotten to the blood, or you start seeing signs of encephalopathy because it has got to the brain. You see she complained about back pains? It is because the cancer has spread to her back. These are all favourable areas for breast cancer spread; breast cancer likes the brain, the lungs, the bones.”
She is clearly a victim of the system. Unlike most patients who report to the hospital late, she sought medical advice once she noticed a lump in her breast in September 2015. After running a series of tests, she was diagnosed with cancer. She promptly began treatment, staying on chemotherapy for six months before going under the knife in February 2017. This was followed by took two courses of chemo after surgery, before enlisting for the botched radiotherapy treatment.
“I didn’t delay treatment at all,” she says emphatically. “Everything was rapid.”
STRUCK DOWN BY INDUSTRIAL STRIKE
She’s not the only victim of the system, though. Of the dozen others whose stories would be touched in this piece, one decides to bare it all. As he explains, there’s nothing left of his human pride. All of it has been “taken away”.
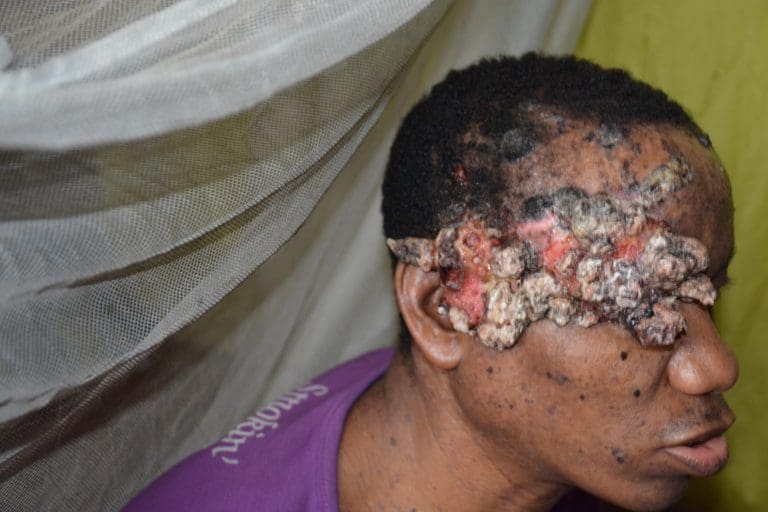
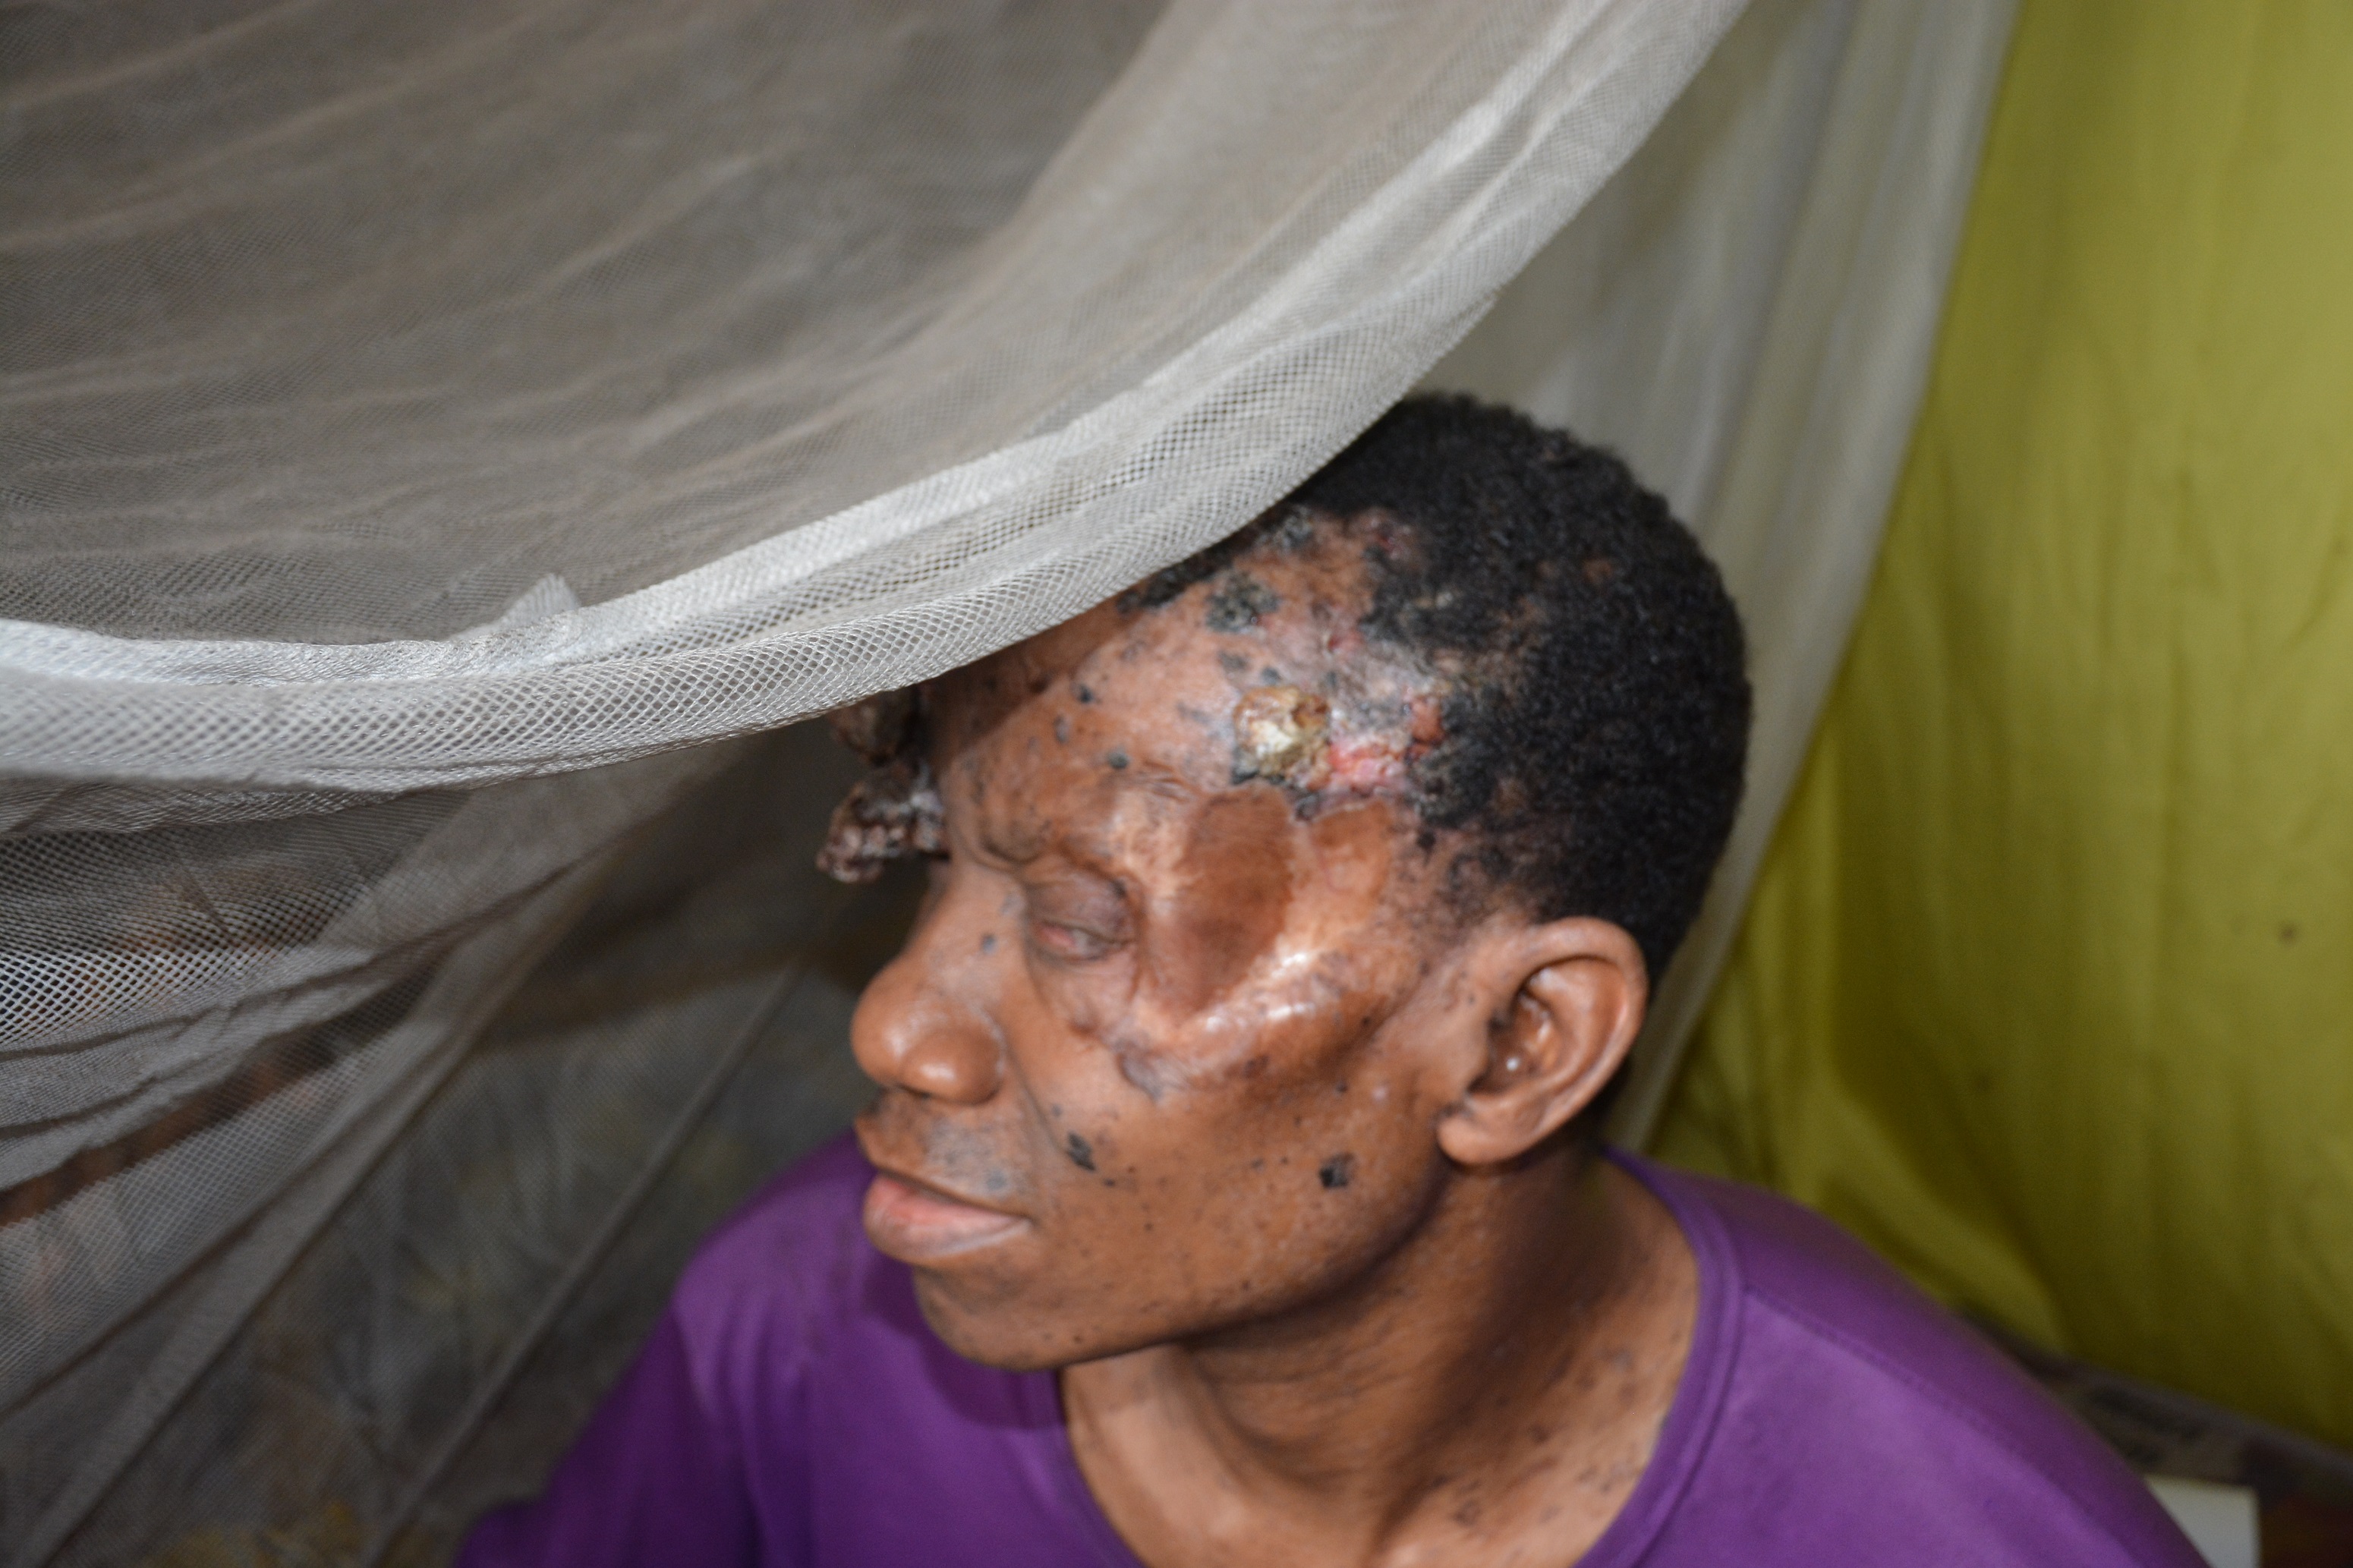
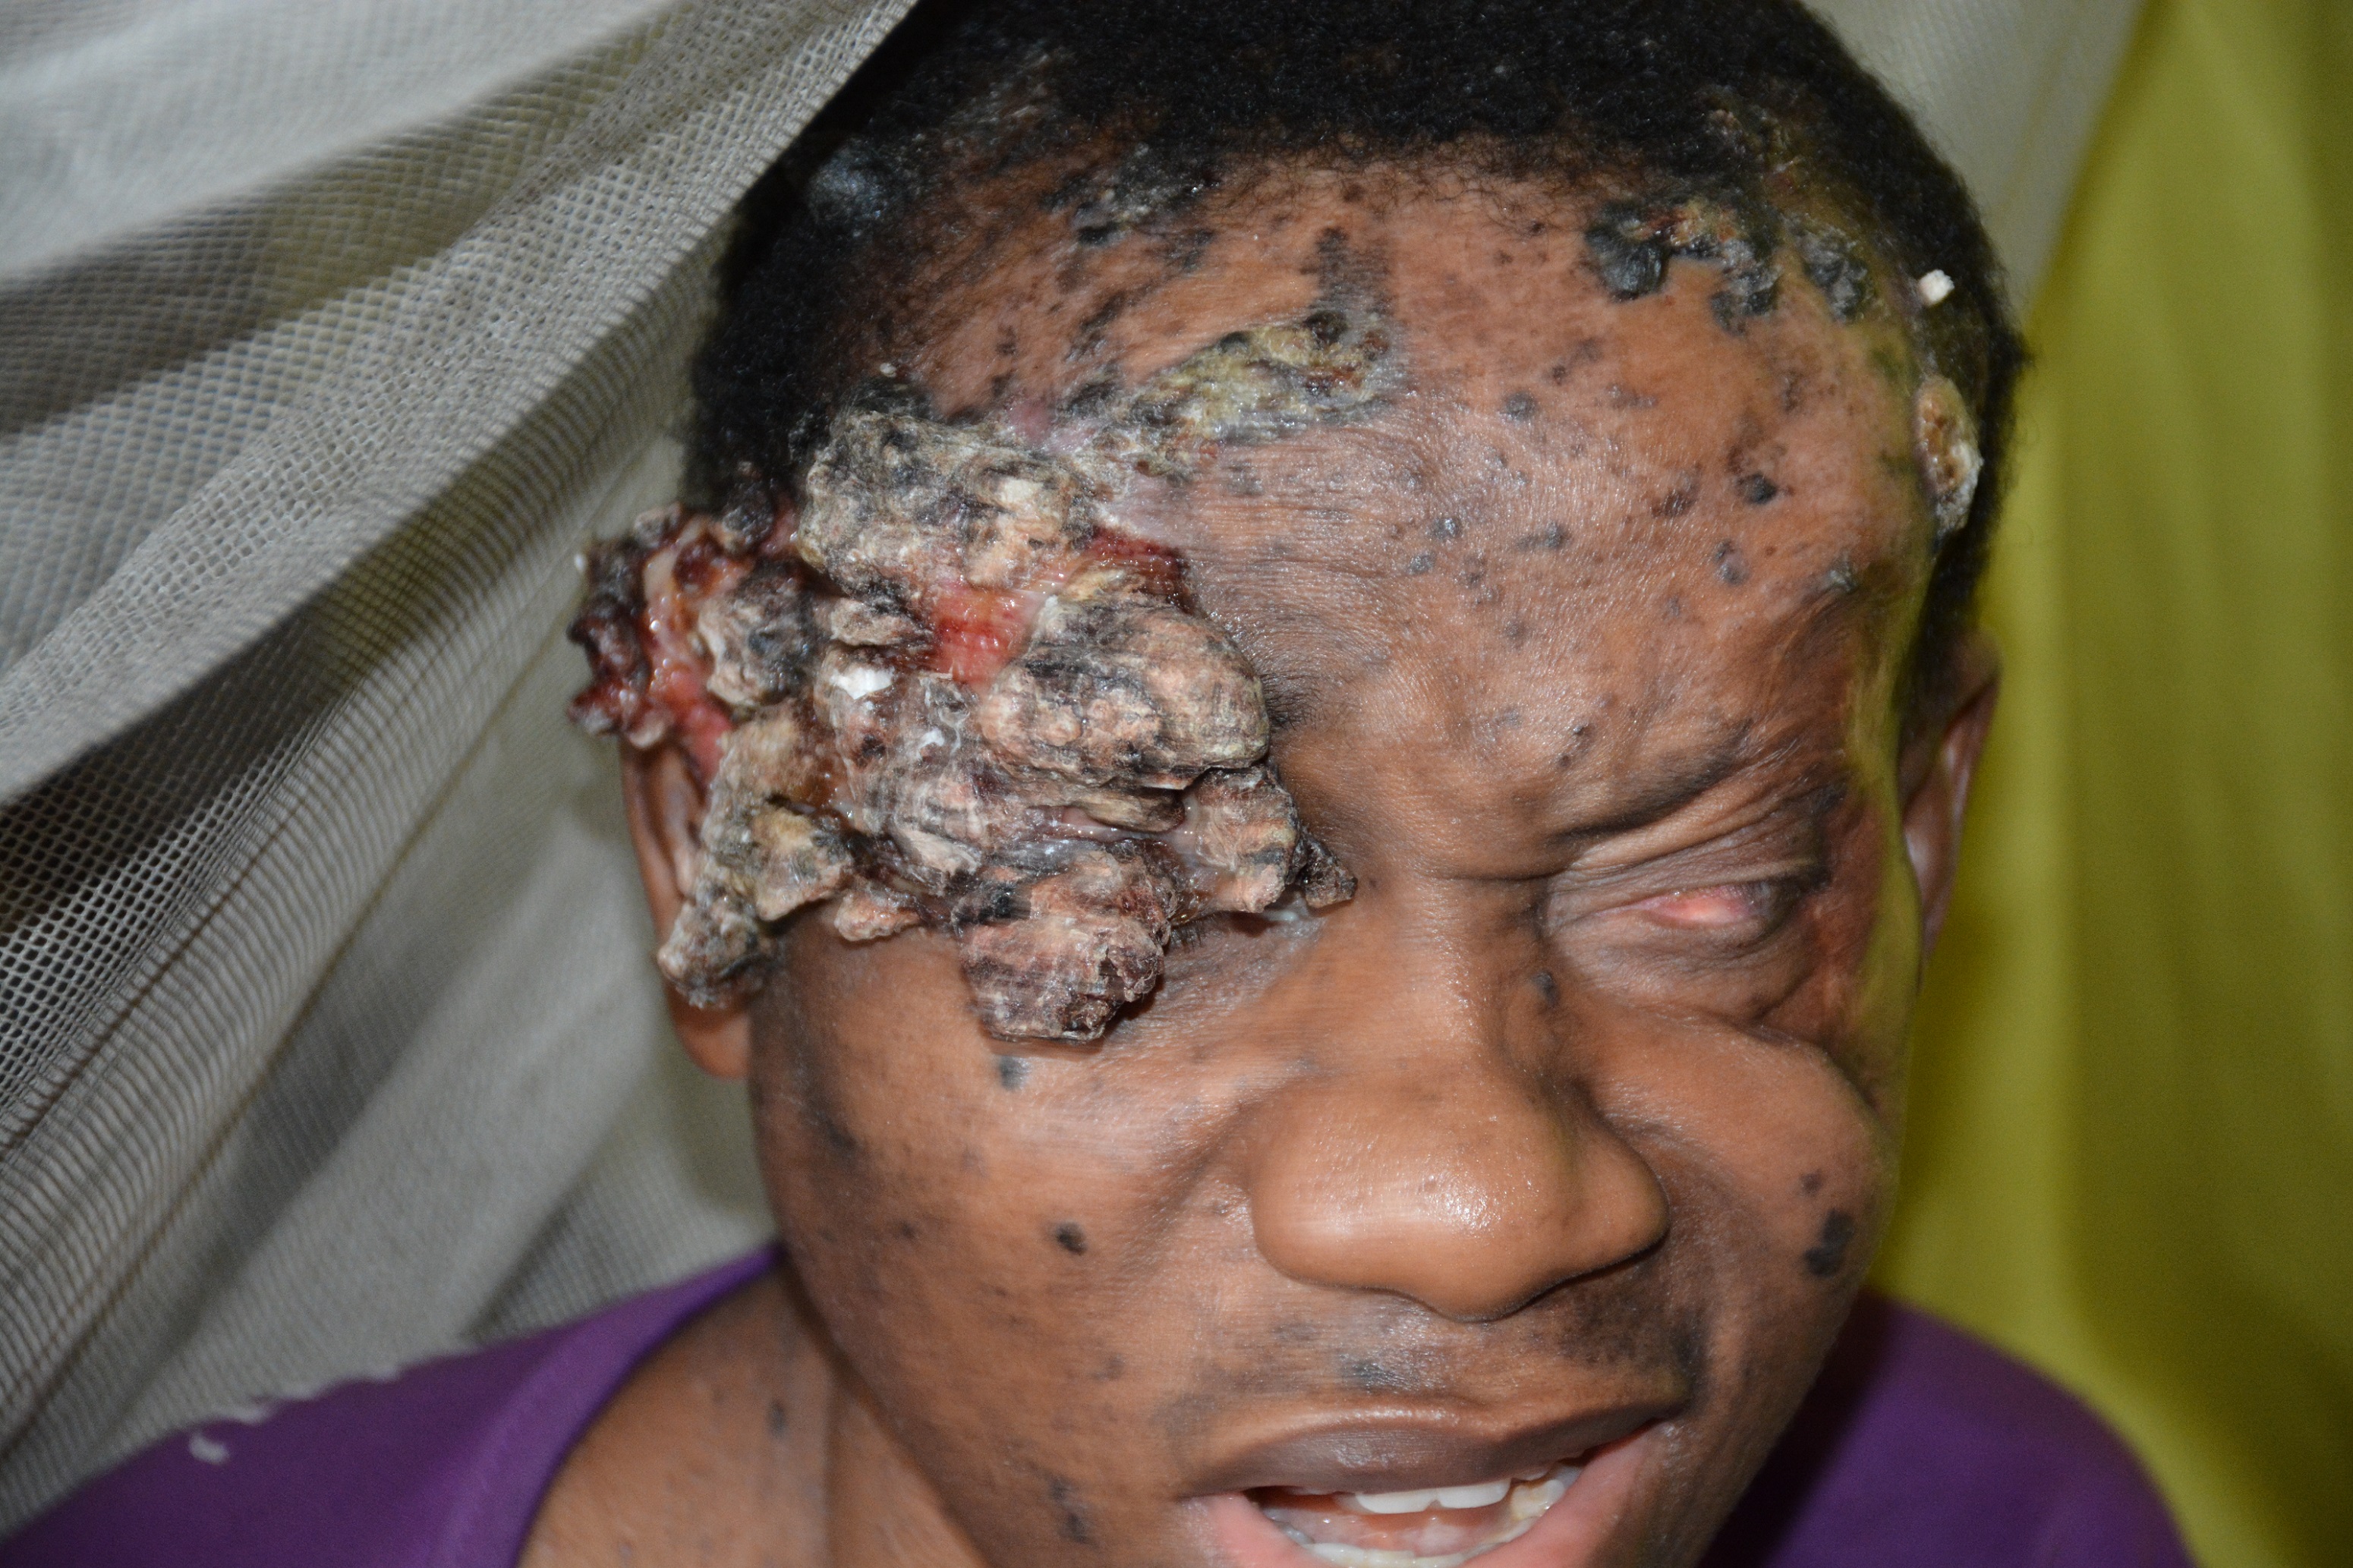
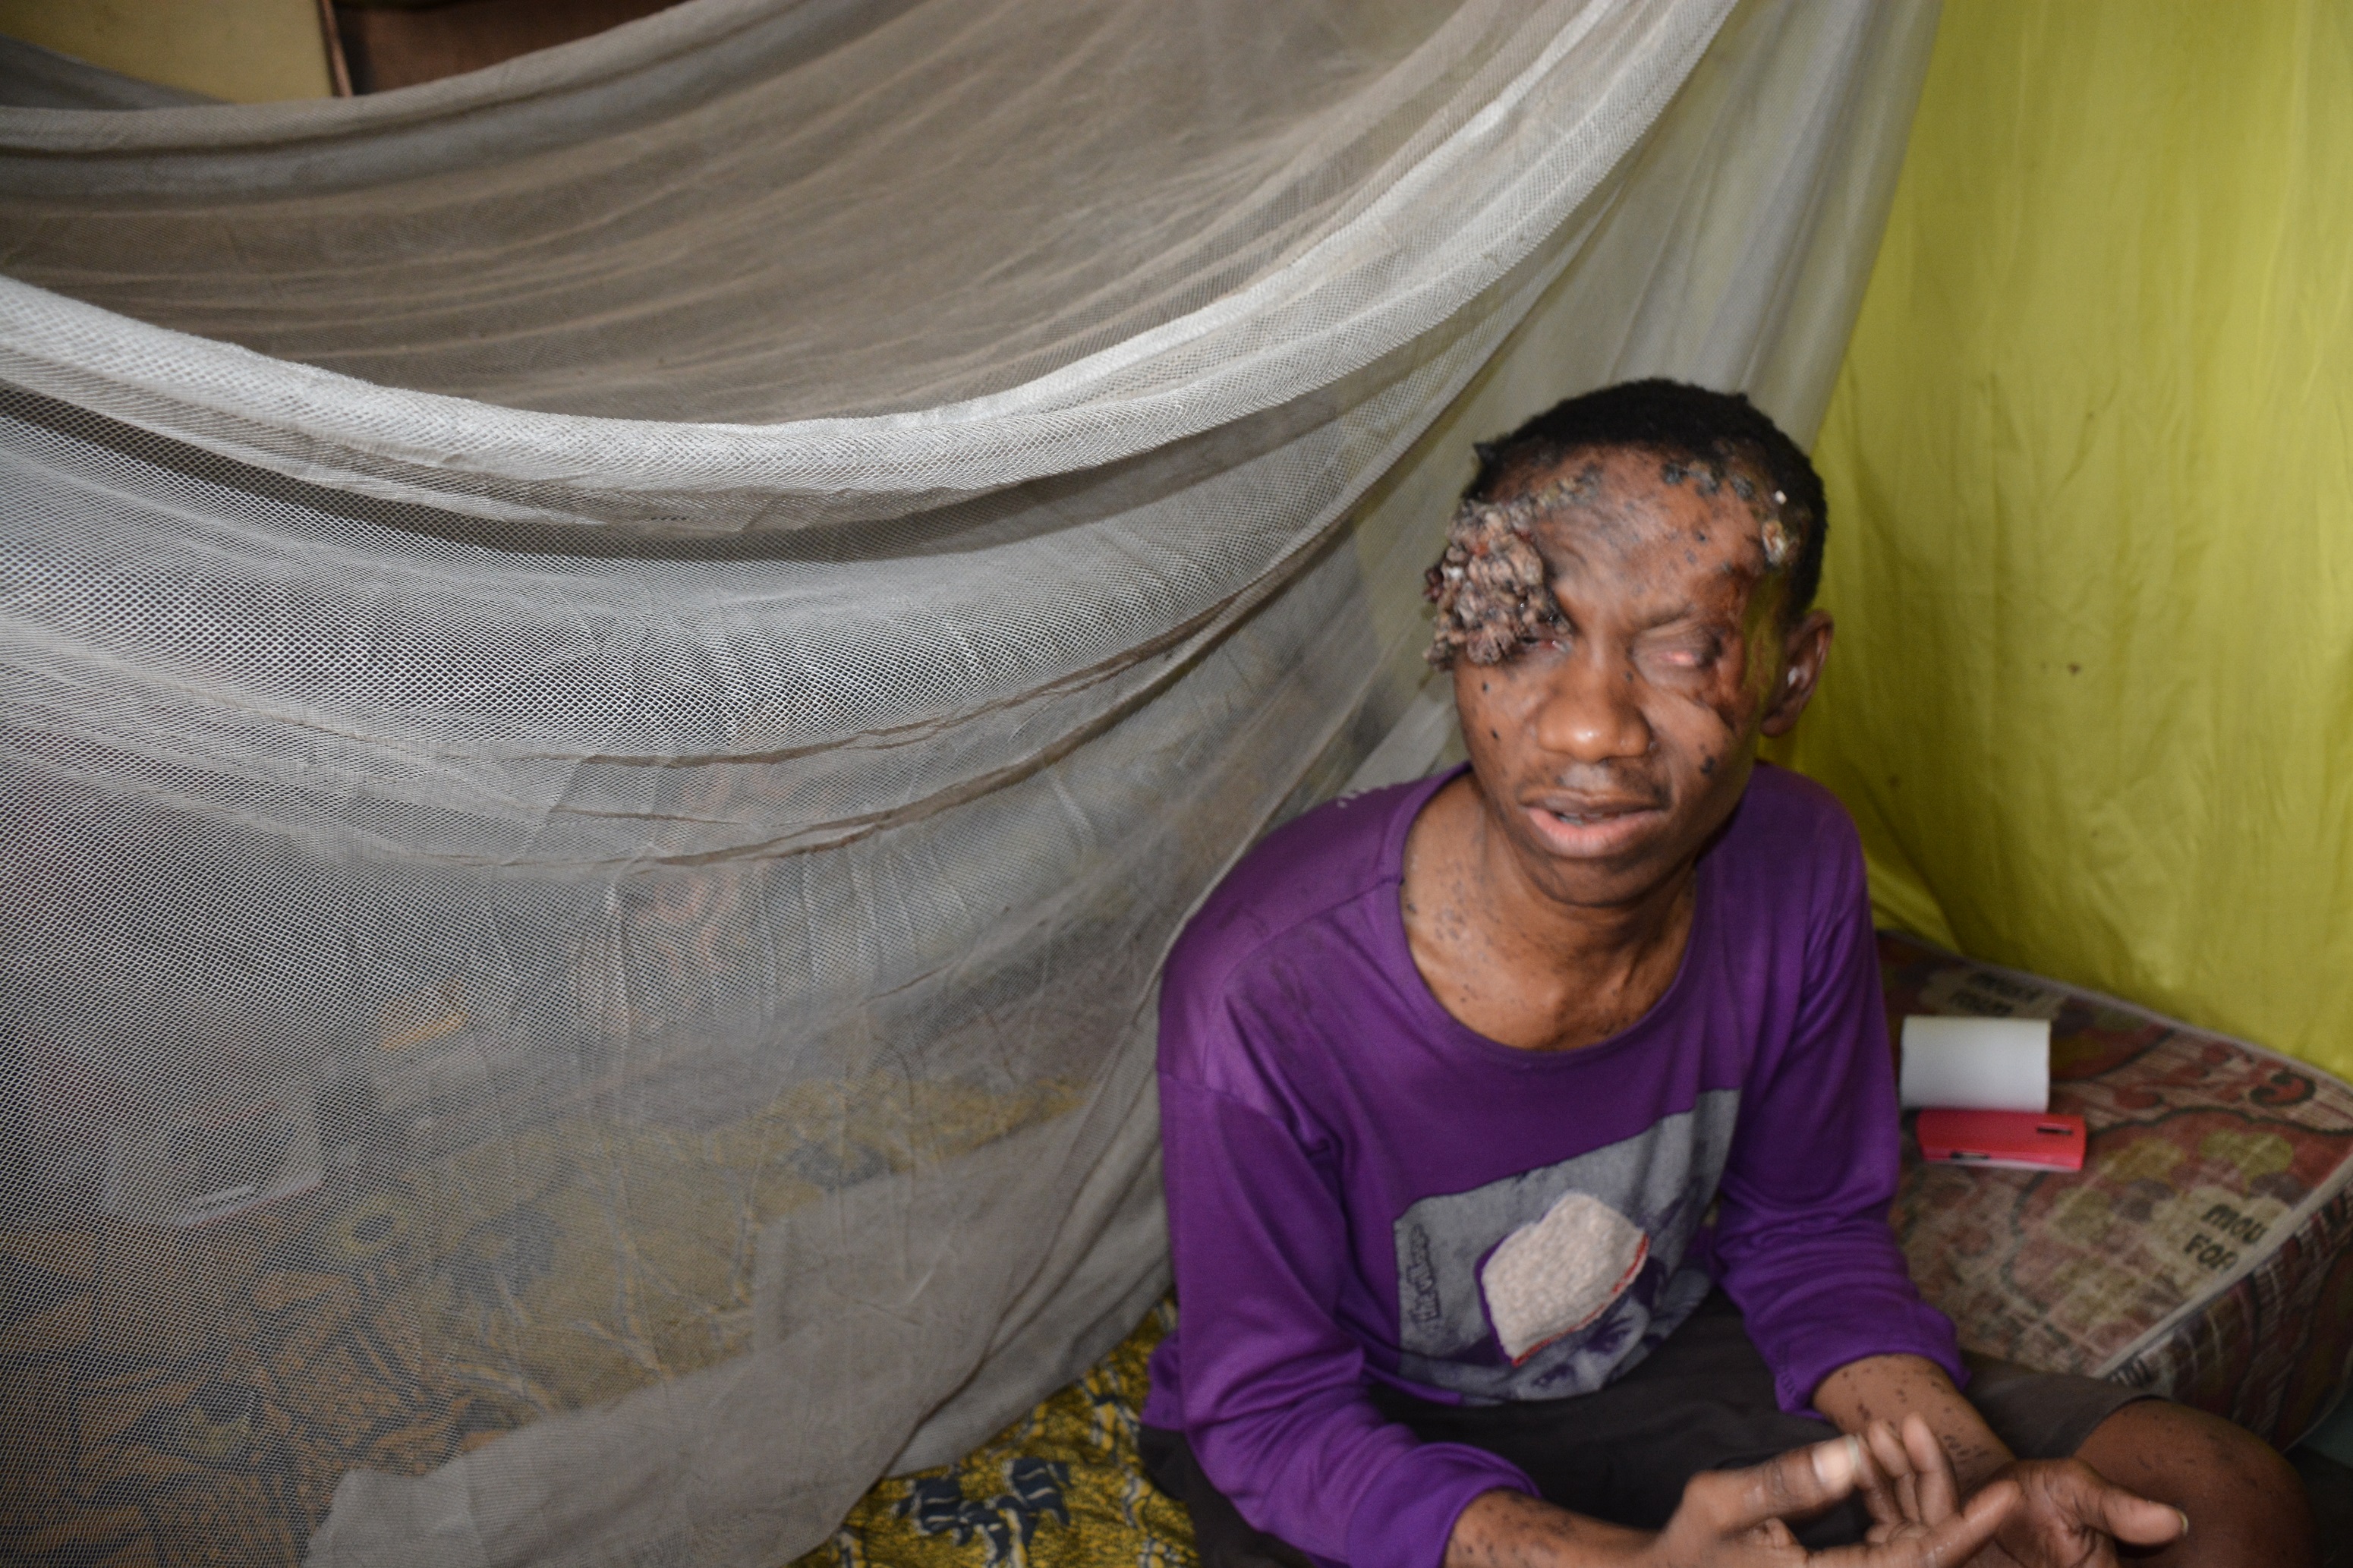
Now 42, Muhammed Musa was only five years old when his parents noticed a small growth around his right eye. It was small but it wouldn’t leave. Best description to give it: “permanent pimple”. As the years passed, it initially didn’t hurt, neither did it rise in bulge. But as Musa approached adolescence, the pimple began to show that it wouldn’t be left out. Then it began to multiply. From the eyelids, similar sights suddenly began appearing on other parts of his body. Rashes! So his mother thought, and thus she sought native treatment in their Village in Edo State.
In his mid-20s — now a man and now in Lagos — Musa sought medical help. Cancer of the eyelids, the doctors said — with attendant tumours that needed to be removed. This was disturbing news because he couldn’t raise the funds. “None of my people had money, as I come from a really poor family,” he recalls.
However, by 2004, he had managed to raise just enough money to remove the tumour. It was a minor surgery. It looked like he had seen the end of his travails. If only he knew that was just the beginning.
Within two years, the tumour was back — this time on the left eye. He had barely recovered from his huge indebtedness courtesy of the 2004 operation. Musa frantically began job-hunting, hoping to be able to save enough to someday fund a second operation. But no one would employ a sick candidate. “That was how I suffered from 2006 till 2010/2011 when I eventually raised the money needed to remove the tumour,” he says.
AN EYE FOR THE SYSTEM
The cancer spread from an eye to another as Musa awaited the end of doctors’ strike actions
Then something heartbreaking happened. The National Association of Resident Doctors (NARD) embarked on a nationwide industrial action, after a series of warning strikes, to “draw the attention of the Federal Government to the deteriorating state of the health sector and low morale of doctors”. As the action coincided with Musa’s surgery date, he missed a big chance. That was in April 2010. Two more industrial actions followed, and on each occasion, the patients were discharged and no one reached out to them upon resumption of work. In all, Musa waited on the doctors for so many months, “almost a year”. Of course, the cancer wasn’t waiting. It spread so rapidly that it cost Musa his eye.
“When I started visiting the hospital, the tumour was quite sizeable, but not so big to the point where it would have affected my eye,” he says in a teary, regretful tone. “But the tumour became overlarge because of the strike action. The doctors would even admit us preparatory to surgery, but there would be strike so they discharged us each time.”
When the last of the industrial action was eventually called off, LUTH didn’t reach out to him. He was “lucky” that the tumour was giving rise to wounds that needed to be dressed, so he went to a private hospital where the wound was dressed for ₦10,500. Subsequent ones were to cost ₦5,000 per session. He didn’t have the ₦5,000 when the second session was due, so he risked an unsolicited visit to LUTH to see if someone could dress the “painful” wounds. “When I got there I met the doctor, and he said they were looking for someone to send to me, that the strike was over and they wanted to perform the surgery. So they gave me a date: March 14, 2011. But the tumour had grown so large that doctors said he would have to lose his eye.
FORTY-TWO AND STILL SINGLE
No wife, no kid at 42. Who will take care of Musa?
Musa eventually went under the knife, sacrificing his right eye for the decay in the system. One more development: his other eye had become badly affected by the wait; so, not long after the surgery, a tumour began developing there as well. In 2013, he was told another surgery would cost him ₦700,000. Unable to afford it, he opted to try the Lagos State University Teaching Hospital (LASUTH), where he didn’t know more bad news awaited him.
“Because the fees they charged was too much, I went to LASUTH at Ikeja. They said there would be consequences if they performed the surgery. One, the second eye would have to go. My ears would stop working. They would remove all the skin on my head, and use another to cover it. That was in 2013,” he explains, tears coursing down his eyes.
“I told them I couldn’t do it — because the left eye had already gone. If I should lose the right one, who will take care of me? Due to this problem, I am still single at 42. I don’t have a wife; I don’t have a child. So who would take care of me?”
‘I’M DYING BUT I DON’T WANT TO DIE’
Musa’s swollen legs
Back then in 2013, Indian doctors told him they could remove the tumour and also save his eyes. But it would cost him N3.8million. but to pay that was someone who couldn’t afford N700,000
By August 2016, the bill had risen to N8.5 million. Without a job, someone to take care of him, or even money to feed, Musa is all by himself at home — somewhere in Oshodi — resigned to fate.
“In June 2017, I started experiencing excruciating pains in both legs; they legs swelled up, and at the end of the day, this one burst. You can see the opening,” he says, then gives in to a cough he had be trying hard to suppress.
“I went to Gbagada General Hospital,” he continues, “but they refused to attend to me. They said I should go back to LUTH, being my first clinic. When I got to LUTH, they said there was no available bed for me, and that they would take me to a private hospital: ₦50,000 deposit first, and ₦1million or more if I spent more than 10 days there. Even ₦5000 I didn’t have on me on that day, where was I supposed to get ₦50,000? from”
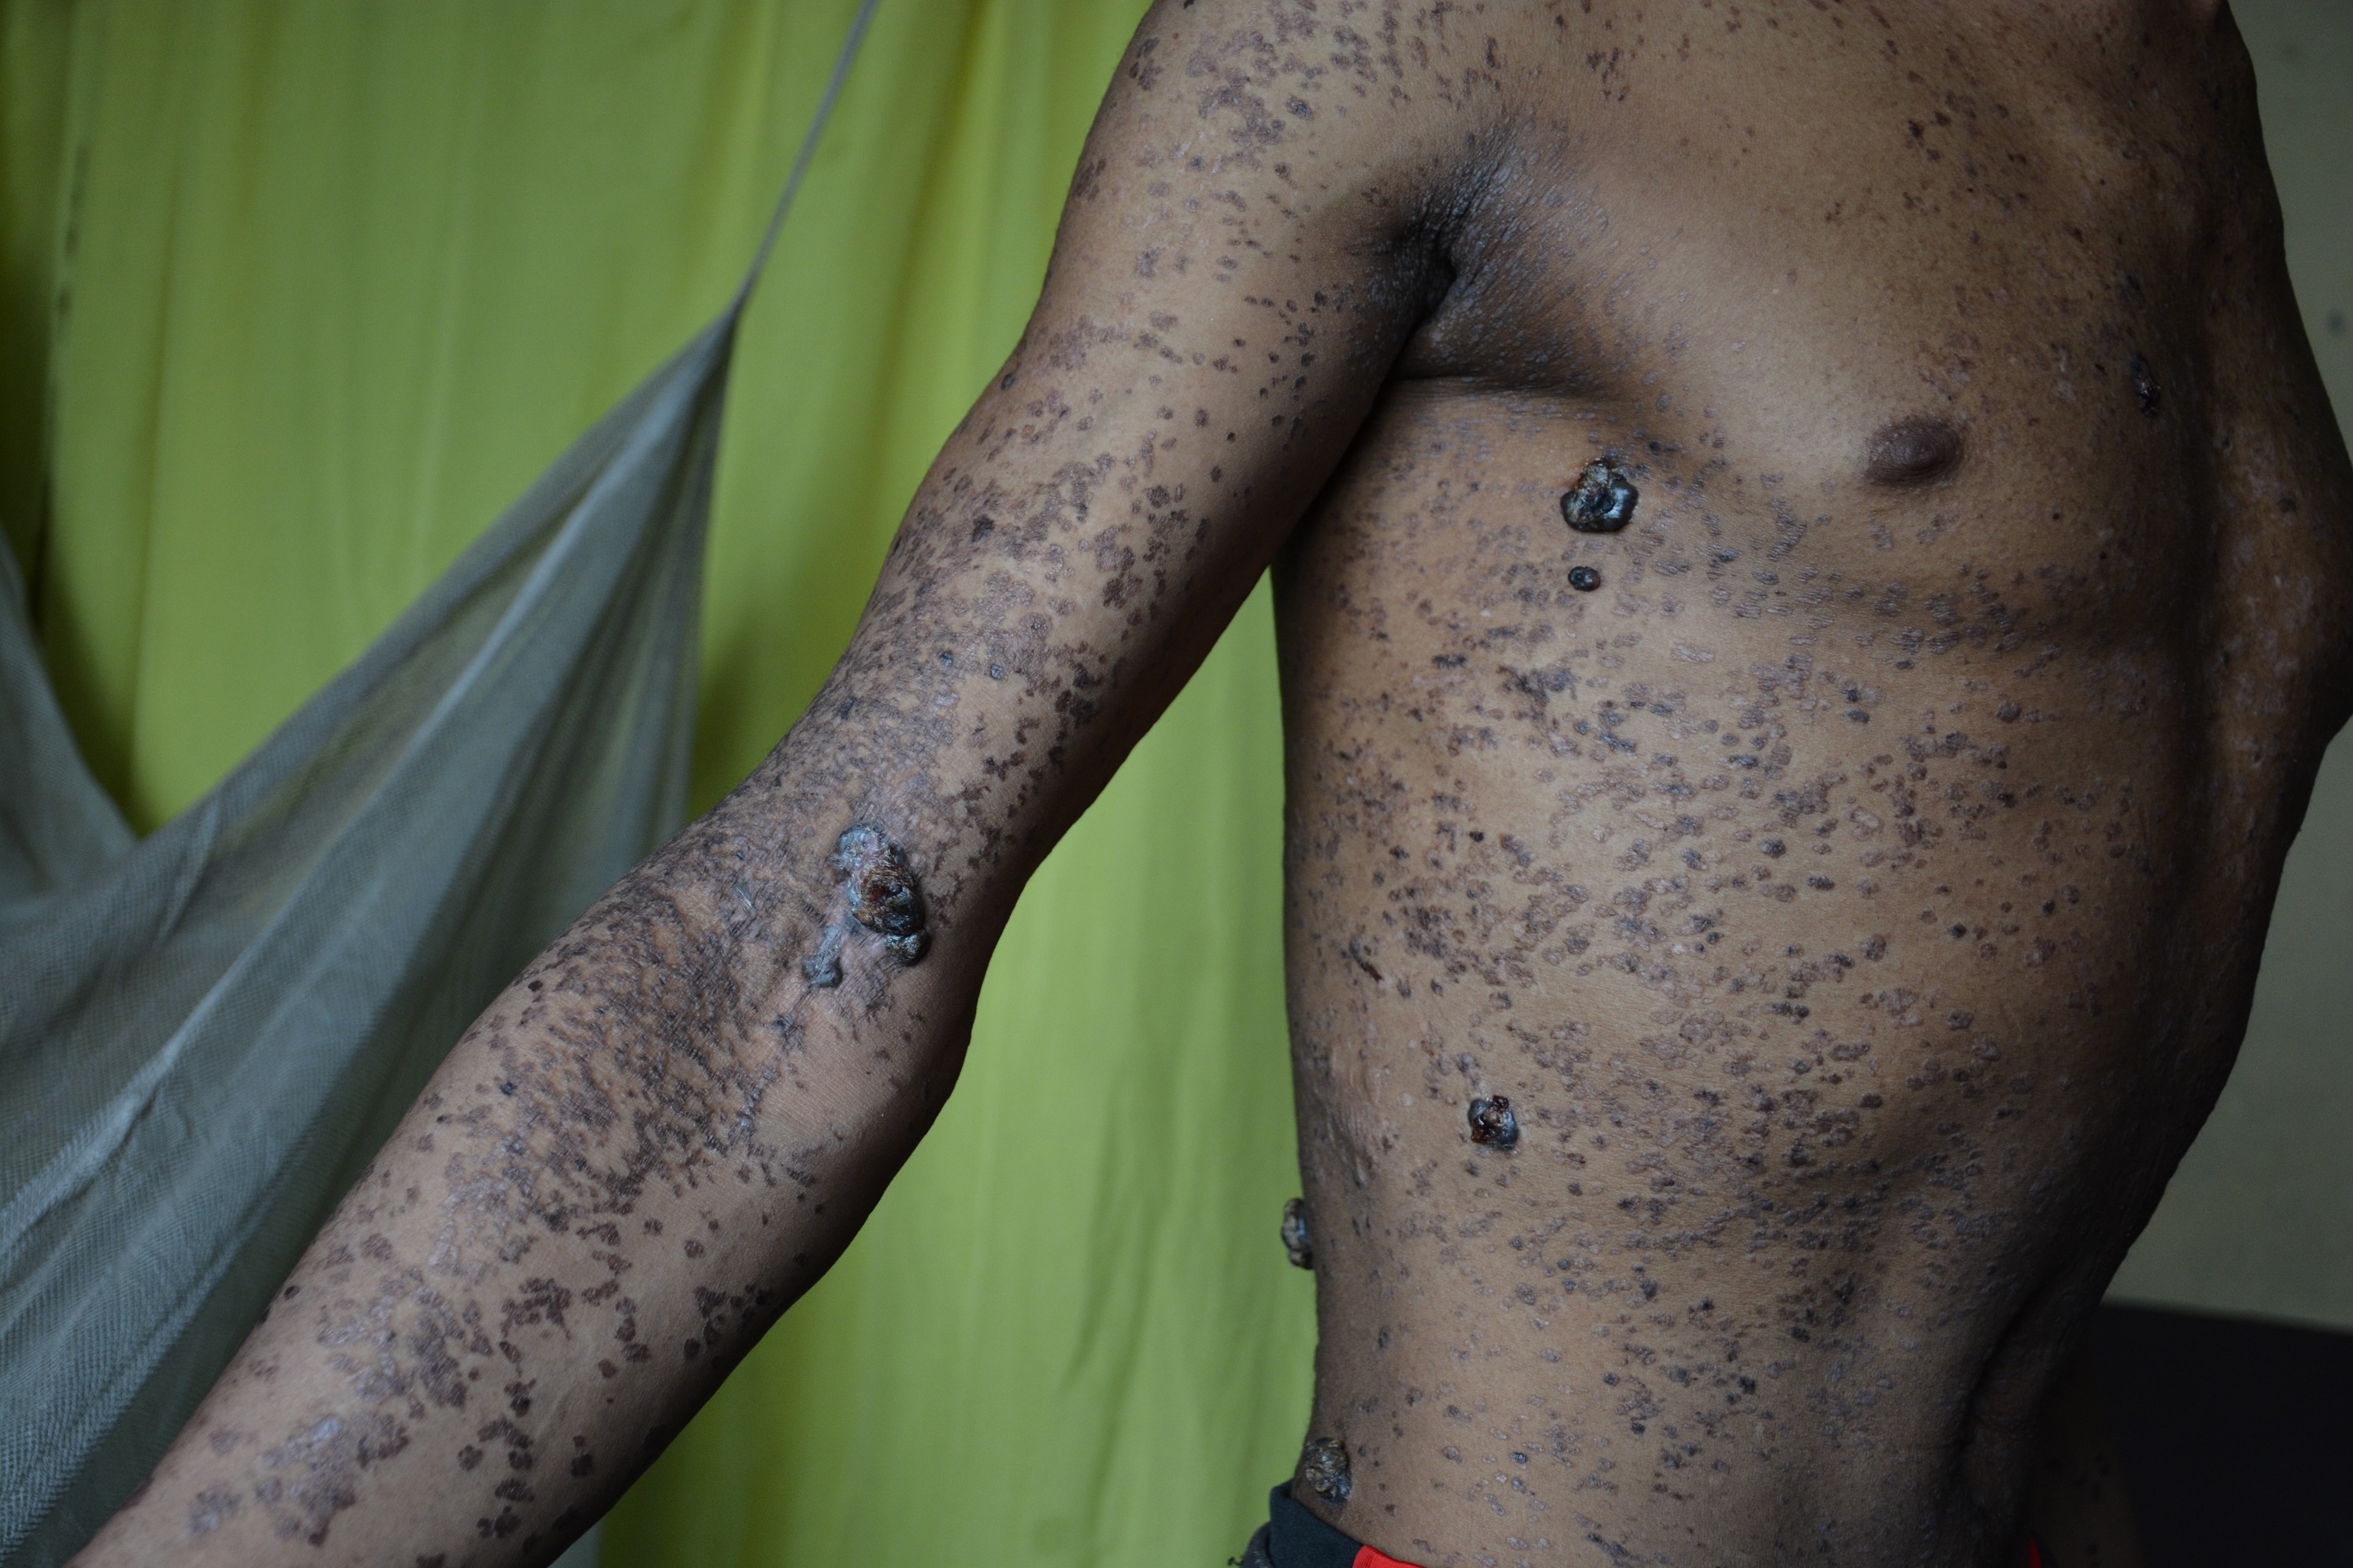
Musa’s problem is beyond the tumour overshadowing his right eye. To prove this, he removes his shirt and folds up his knickers, revealing spots of rashes and tumours marauding his skin. A thick stench at once rents the air at the penthouse from which the landlord is already threatening to eject him for defaulting on rent.
NO FOOD, NO WATER, FAILING HEALTH
More tumours are appearing on Musa’s body, and they’re growing fast!
“I’m sorry, my brother, but I have nothing to hide any longer. If I die today, the people who will bury me will get to see the nakedness I’m hiding. Look at me, I’m dying here but I don’t want to die. Please help me,” he says tearfully.
“I’ve run everywhere possible… no one to help. I wrote to the Ministry of Health; I wrote to the Lagos State government. They said they had no funds to assist me. My brother, I swear to God, since yesterday, even sachet water I have not seen to drink.”
Musa did get some help along the way, though. A house officer at LUTH picked interest in his case, and continued sending him money even at the expiration of his housemanship and relocation from Lagos to Ibadan. That doctor is now jobless, and as such, Musa is feeling the heat.
“It is only this doctor that has helped me when capable. But since he lost his job, I have been in a bad situation here. It is only if someone remembers me and decides to visit, maybe one of my mosque members, that I get something to eat.”
The bad news is that it looks his condition may get worse. He knows as much, admitting: “You know, these skin rashes have now started developing tumours; the doctors said they have stayed too long on my body. The only thing they can face is the tumour on my eyes. And when they’re done facing that one, we will be dealing with more tumours from those rashes.”
NO RADIOTHERAPHY IN LAGOS, NO BIOTHERAPY IN ZARIA
“Please help me, please help me,” a 64-year-old woman says in Pidgin English amid fits of cries and screams. “Doctor, abeg make una help me oooooooooo.”
Were the basic cancer treatment procedures in place, this woman would have no business with admission at LUTH’s gynecology ward. By the woman’s account, LUTH referred her to the Ahmadu Bello University Teaching Hospital (ABUTH), Zaria, to undergo biological therapy (biotherapy for short) — a type of treatment that uses substances made from living organisms to treat disease. Biotherapy is considered superior to chemotherapy because chemo drugs can’t differentiate between cancer cells and healthy cells in the body. As a result, chemotherapy causes damage to normal cells, which can result in nausea, fatigue, hair loss and other side effects associated with this type of treatment. Biotherapy, meanwhile, generally makes use of natural, living substances that bolster the immune system’s ability to fight cancer. In addition, some forms of biotherapy prevent specific cancer cells from growing, or even kill them. Compared to other cancer treatments, the side effects of biotherapy are notably low.
After listening to the woman, the undercover doctor explains what the LUTH doctors must have been thinking, in sending the woman to Zaria. “Sometimes, as a doctor, you assess some patients and you see clearly that there is a limit to the external gimmicks that you can make. So you complement with biotherapy.”
Worried by how her two children, both adolescents — one male, the other female — would survive should she die — the woman, a roadside roasted plantain seller at Ojo-Alaba, Lagos, borrowed money and endured a tumultuous road trip to Zaria from Lagos. Without enough money for hotel accommodation, she slept out in the cold during her few days in Zaria. That was in 2016. On arriving the teaching hospital in Zaria, she was told, first, that they were not expecting any patient from LUTH. The LUTH authorities hadn’t pre-contacted them. This could have been sorted out in a matter of days, but the bigger problem was that Zaria’s biotherapy machine had broken down.
“It’s not only Zaria; I know two teaching hospitals in Nigeria with the equipment to carry out biotherapy, but none of them as functioned in the past three years,” the undercover oncologist adds. “In fact, presently, there is no functional biotherapy equipment in any public hospital in Nigeria. Long and short, biotherapy is currently unavailable in Nigeria — and this is a function of equipment, not expertise.”
Ever since, the woman has been frequenting LUTH for drugs, tests and admission. But, on the evidence of current pains, the cancer in her cervix is spreading fast.
‘I DON’T WANT TO DIE… MY CHILDREN ARE STILL IN SCHOOL’
“Since then, I have been constantly complaining, especially regarding my stomach. It’s getting bigger and the pain is so much,” she says, again in tears. “I have spent a lot of money too, and on many scans that cost ₦40,000, ₦30,000 each. There is nothing, including scans and injections, they recommended that I have not done or bought, but my belly is swollen now and won’t return to normal size.”
The woman bursts into another round of please-help-me tears. The stomach aside, her left leg has swollen up. Various scans on the leg have yielded no solution. She is also one of the victims of the breakdown of LUTH’s radiotherapy machine; she had only completed a little more than half of the recommended radiotherapy sessions when the machine broke down in June 2016. Twice — with biotherapy and radiotherapy — this country has failed her. And this is after spending well over N1million on her health. Bear in mind that this is a roadside roasted plantain seller, and that the stomach and leg swellings and pains weren’t there pre-Zaria, when she first reported to LUTH.
“Please help me,” she sobs again, louder this time, as undercover oncologist and doctor make their way out of the ward. “Please, help me. It is the small money I make from my work that I use to send my children to school. I don’t want to run out of funds for their education. I don’t want to die while they’re still in school.”
A DAY AT LUTH’S ONCOLOGY AND RADIOTHERAPHY DEPARTMENT
LUTH’s oncology/radiotherapy department… early in the morning
On an average day, the Oncology Department at LUTH is like a tripartite arena. First part, early in the morning, it takes on the semblance of a graveyard. We’re talking 7:00, 7:30, 8:00am — cancer patients, old and young, male and female, are trickling in, some for confirmation of next laboratory tests, some for the highly-dreaded chemotherapy sessions, others for confirmation of surgery dates or for post-surgery evaluation.
The ward is generally quiet at this stage, save when the familiar faces of long-term patients interlock, paving the way for exchange of mild-witted niceties. Globally, cancer is a generally deadly disease. But Nigeria is where the death ratio is highest: 805 of 1,000 cases — or four in five cancer cases — result in death. According to statistics from the World Health Organisation (WHO), over 100,000 Nigerians are diagnosed with cancer annually, with 80,000 of them dying from the disease — an average of 240 Nigerians/day or 10 Nigerians/hour. As if that wasn’t enough, WHO has predicted that Nigeria can expect a 75 per cent increase in cancer-induced death by 2030. Add that to the chaotic and comatose health system and it can be said that in Nigeria, cancer is somewhat a death sentence, the reason the oncology ward usually wears a sombre, gloomy look early in the morning.
Usually, from a few minutes past 8am till 10am or thereabouts, a first-time visitor can be forgiven for thinking he missed his way and ended up in a church! This is the second part, comprising praise and worship, sermon and altar call. Then the third and final part is where the ward looks both like a hospital-cum-market: filling the attendance list, roll call of patients, loud complaints by angry patients.
When the journalist visited the department one Thursday in March, all three scenarios played out. First, the initial silence. But at 8:20am when a nurse comes in and tells the patients ‘Let us pray’, everything changes. After the prayer comes a praise and worship session that begins thus at exactly 8:55am: O se o Jesu/a o ma yin o/o se o Jesu/Olorun ayo wa (Thank you Jesus we will praise you, the source of our joy…). Soon, nurses and patients invite God to their midst to perform miracles, singing: Yahweh/Your name is Yahweh/You are the miracle working God/Your name is Yahweh, and later Come and do your miracle today/Your miracle today….
One look at the patients and one could tell they looked more to God for help than to the doctors at LUTH. And it is easy to see why: those of them scheduled for radiotherapy sessions understand that the doctors can do no magic if the government continues ignoring the hospital’s broken-down RT machine. In any case, the nurse leading the session soon touches the matter as praise and worship morphs into full-blown prayers. “Let us continue to pray for Nigeria and for our government,” she charges the patients. “It is our right to have this radiotherapy machine but unfortunately our government is not up to date in this wise. We are optimistic that things will improve very soon, but we must pray so this can happen quickly.”
The end of prayers at 9:22am isn’t it for the day, no. A female doctor — tall, fair and with a thick Igbo accent — takes over. It’s sermon time! It lasts approximately 20 minutes and is followed by the altar call: those who want to surrender their lives to Christ have the chance now. Of course, for a population of people afflicted by a disease that translates to a death sentence in their country, quite a number presented themselves. Who would blame them? Better to hand one’s live to Christ since Nigeria places no value on it, anyway. Altar call ends at exactly 9:49am; time, now, for the day’s main activities.
As the patients watch out for their names to have their moments with the doctor, there is a huge conversation about how the lack of a radiotherapy machine at LUTH was compounding their woes. By the accounts of five patients, private hospitals are taking advantage of the gap.
HELPING PATIENTS SEE DOCTORS IS LUCRATIVE BUSINESS
“I went to Eko Hospital after the breakdown of LUTH’s machine, and I was given a bill of N160,000,” says a slender, light-skinned woman. “But when I presented myself on appointment date, I was told that the cost had risen to N250,000. Apparently, Eko Hospital had become aware of the damage to LUTH’s machine, so they saw an opportunity to make quick money.”
“It’s blood money, I tell you!” another patient yells. “My own problem is that Eko Hospital is crowded these days; it’s so difficult to see the doctors.”
Having devised an underhand way around the challenge, the first patient offers some interesting advice: “There is this boy who lives not so far from the hospital; if you give him N500, he’ll go there around 2 or 3am to write your name on the patients’ list for the day. I can link you to him if you want, but that’s what I do.
“I started doing it since the day my husband and I spotted robbers around Jakande and Lawanson [on Victoria Island] when we left home around 4am because I needed to see the doctor early. We had to stop doing that; we won’t die before death comes.”
Were the boy to do that for 10 patients every day, that’s N5,000 daily — N25,000 at the end of the week.
Their conversation is interrupted by a woman who left her home in Ikorodu at 5am so she could arrive the hospital in time to see the doctor, but has now been told, at 11:06am, that her file is missing.
“What manner of nonsense is this?” the woman, dark, ostensibly in her mid-30s, says. “Can you imagine such utterance? As if I took my file home the last time!”
She returns to the hospital staff after 15 minutes but she is told to “stop disturbing us”. “This people are trying my patience,” she huffs. “I will leave them to their madness and go to my home, after all it is God who takes care of the sick.”
After about an hour of tussle, she is told to see the doctor; the file would be taken care of later.
File disappearances aren’t specific to LUTH. According to a doctor, who asked not to be named because of her close ties to the UCH, such disappearance once cost a patient’s life — indirectly.
“Few years back while working at UCH, I had this patient whom I suspected had breast cancer. But to be 100% sure, I sent her to the lab,” she recalls. “She did the test, but when the time came to collect it, UCH couldn’t find her result. She was told to pay a second time for another test.
“But this woman never came. Instead, her church members convinced her to focus on prayers. Guess what, she eventually died of cancer. If UCH hadn’t lost her test, she would have started treatment fairly early, and maybe she’d still be alive today.”
AT UCH, NO CONNECTION, NO RADIOTHERAPY
On his sick bed at the University College Hospital (UCH), this 54-year-old suffering from cancer of the anus cuts a frustrated figure. Since relocating to UCH in February (and this is March), he has taken in five pints of blood — in addition to seven at LUTH. And he has suffered. Each time he tries to talk, he finds that the strength left in him isn’t up to it. Then he resorts to tears. “I know I will get well,” he says intermittently, “and when I get well…”
His wife always cuts in: “Relax, honey; you will be fine.” She is his spokesman now. Not just that, his number-one caregiver, his manager, his comforter, his pillar. Another classic example of how listless life would be without love — how, without love, hospitals would be faster pathways to the graveyard.
“He was rejected at LASUTH because there was no bed space,” the undercover oncologist and journalist, who had found their way into UCH through the backdoor, overhear his wife say to a friend on the phone.
Even at LUTH, there was no bed space. But seeing how badly he needed to be admitted, the doctors took the difficult decision of searching round the ward to see who could be discharged. Finally, they found someone whose condition they thought was the least critical, and sent him home; but ordinarily, that patient would have remained on admission.
That admission at LUTH was short-lived, though. He needed radiotherapy and was told the machine would “soon” be repaired, but the wait was becoming endless. Earlier, he had also waited on the radiotherapy machine at the University of Nigeria Teaching Hospital (UNTH), Ituku-Ozalla, Enugu, for more than a month, but was eventually told it was “bad”. No longer willing to take risks, he decided to try UCH. But there was still one problem: it was January but UCH’s radiotherapy machine was already booked till April! Luckily, after his wife called a doctor-friend of hers, they received an expedited appointment. They arrived UCH in February, after more than three months of rejection by LASUTH and waiting on UCH and UNTH.
And so, while Eko Hospital is profiting from a lack of radiotherapy machine at LUTH, UCH is smarting from it. At UCH, there is increased competition for the machine to the extent that non-UCH patients have no chance of going under its radiotherapy machine early enough unless they’re connected to the hospital’s hierarchy.
On his sickness, they have spent more than N2million — more than half of that due to the endless wait for the machine. “We spent a lot of money on tests and drugs just to keep him in shape pending the readiness of the radiotherapy machine,” she says. “SO far, he’s had five radiotherapy sessions. Hopefully, he can get well soon.”
There are only four functioning radiotherapy machines all over the country to serve an estimated 200million Nigerians, yet the International Atomic Energy Agency (IAEA) recommendation is one RT machine per 1million people, meaning Nigeria should ordinarily have roughly 200 RT machines.
Of these four functioning machines in Nigeria, one is owned by Eko Hospital, a private hospital. This means that of the 20 federal teaching hospitals in the country, only three — UCH, Ahmadu Bello University Teaching Hospital Zaria and the National Hospital Abuja — currently have functional radiotherapy machines. The Usman Dan Fodio University Teaching Hospital Sokoto (under repairs), UNTH and LUTH have, but the machines have been down for varying long periods of time — that’s having like not having!
To put the situation in perspective, 17 of Nigeria’s 20 teaching hospitals cannot offer radiotherapy to cancer patients. Also, radiotherapy is unavailable in the entire South-South (comprising Akwa Ibom, Cross River, Bayelsa, Rivers, Delta and Edo states). Anyone diagnosed with cancer in this region must travel out of it — either to Enugu in the South-East, Lagos or Ibadan in the South-West, or Abuja in the North-Central. This trend is nothing new; there was a time in 2015 when only two radiotherapy machines were functioning in the whole country.
‘OLD SCHOOL’ RT MACHINES
A cobalt-60 RT machine purchased in 2017 by the Ugandan government
Painfully, of the four radiotherapy machines available all over Nigeria, only one — National Hospital Abuja’s — is useful for curing cancer; all other three cannot. They are only useful prolonging a patient’s life; more like ‘you’re going to die anyway but let’s try not to make you die too soon’.
So explains Runcie C. W. Chidiebe, a cancer control advocate and Executive Director, Project Pink Blue.
“The radiotherapy machines at Zaria and Eko hospital are cobalt machines,” Chidiebe moans.
“I have interacted with so many medical physicists, clinical oncologists and radiation oncologists, and they will tell you that the beam produced by cobalt radiotherapy machines is not sufficient to prevent spread or even ensure any treatment or therapy; it is just good for palliative care only — that is the situation whereby you’re no longer trying to achieve cure but just to prolong the patient’s life.”
Chidiebe was stunned to find out during a recent visit to Texas Oncology in Sherman, in US, that just one centre had two radiotherapy machines — one variam, the other linac accelerator — serving 100,000 people.
“None was cobalt!” he exclaims. “These are the newest machines that produce sufficient beams that can really contain the cancer and prevent it from spreading to other vital organs.”
THE RADIOTHERAPY HUSSLE IS REAL
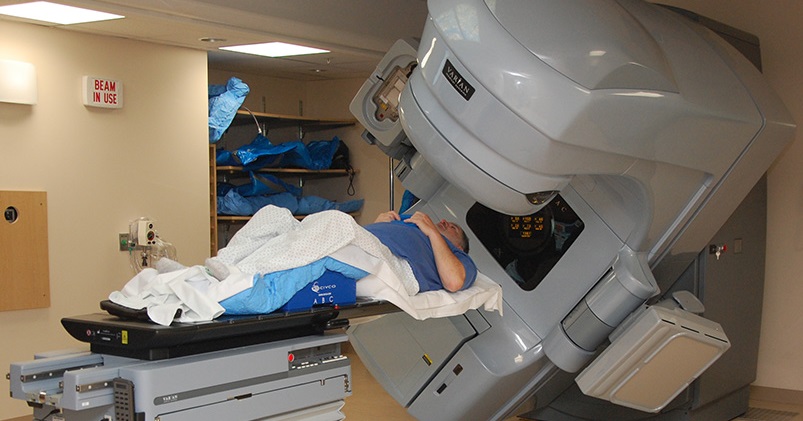
A varian linac RT machine in use at the National Life Cancer Treatment Centre of the Central Vermont Medical Centre, US
An expected consequence of the scarcity of RT machine is the huge competition for sessions in the three hospitals where the service is available. In those hospitals, an appointment is extremely difficult to secure, and officials try their best not to offer guarantees on the stability of their RT machines.
“The machine is working,” a UCH official said on the phone when asked for how soon an appointment could be booked, before quickly adding emphatically: “as of today!”
A contact in the radiotherapy department was supplied, and, although the doctor at the other end hesitated to pin a date for a patient that hadn’t been physically examined, he eventually said: “If the patient comes and we discover that it is not an emergency, he cannot get a RT appointment before July.” That is four months of offering the cancer unfettered access to spread!
FINANCING FOR ONCOLOGY MUST IMPROVE
Chidiebe laments: No bone scan working in the entire country
So, what can be done to bolster the quality of treatment available to cancer patients, particularly in terms of access to RT?
“Most of the RT machines break down intermittently,” says Chidiebe. “Some don’t even work up to one month. It takes months to get money out for maintenance, but cancer doesn’t wait; it keeps spreading. We have refused every year to invest in cancer control. Financing for oncology and radiotherapy is so poor; it has to be improved.”
Another step, he explains, is for government to buy the machine spare parts and keep them, instead of waiting for the machines to develop fault.
“As I speak to you, there is no bone scan working across the country. We have two bone scan centres — UCH and National Hospital — but the problem is that there are no reagents,” he says.
“Can you imagine? The machines are there but no reagents. Isn’t it shameful? The nuclear medicine guys have to travel to South Africa to get these things. The Nigeria Customs Service are not helping issues, too, with the way they frustrate you with their corrupt demands when you try to bring these machine in.”
WHERE IS THE MONEY???
Adewole, Health Minister
The most expensive linac radiotherapy machines cost between of $750,000 and $1.5million (between N228 million and N456million, at the current CBN rate), excluding associated costs such as the vault that will house the system, treatment planning and oncology information system software, lasers, and other accessories.
However, only N55.6 billion was allocated to capital projects in the ministry of in the 2017 budget. In 2016, it was N28.7billion, N22.7billion in 2015, and N49.5billion in 2014. In 2017, a total of N4.01 billion was budgeted for all 20 teaching hospitals; it was N2.4billion in 2016, N1.8bn in 2015 and N9.3bn in 2014. That’s grossly inadequate, considering the enormous equipment deficiencies of those institutions, which perhaps explains why University of Port Harcourt Teaching Hospital, despite receiving the biggest share of the 2017 capital allocation (N492.8million), still doesn’t have a RT machine.
While the health sector is incontrovertibly underfunded, it would appear that the bigger problem is financial mismanagement, not under-funding. In the 2017 budget, N9 billion was specifically allotted to the purchase of radiotherapy machines for some teaching hospitals (and another N117 million was also budgeted for cancer-related issues).
Let’s make two unlikely assumptions: that the government purchases the most expensive linac RT machine in existence (N456million) and the associated costs are as expensive as the machine itself (another N456million). This would mean that at the very maximum, one RT machine would cost N912million. Therefore, the N9bn budget would have funded the purchase of nine radiotherapy machines.
But in 2017, the government bought only one RT machine — for the National Hospital! The question, then, is: where is the rest of the N8bn?
This was one of the many questions that would have been put forward to Isaac Adewole, a Professor of Gynaecology and Obstetrics and Minister of Health, and Osagie Ehanire, Minister of State for Health, but neither responded to the email and text message sent to them.
THE LONG-TERM SOLUTION
Universal Health Coverage (UHC) is the long-term solution, says Pink Oak’s Laz Eze
Dr. Laz Ude Eze, Executive Director of Pink Oak Cancer Trust — an NGO that raises funds to help cancer patients access better care — cannot understand why Nigeria can’t reproduce the success of even neighbouring African countries in making quality care available to cancer patients.
He recalls — and adds that “it is shameful” — that when all the radiotherapy machines in Nigeria broke down, Nigerians were travelling to Ghana for radiotherapy.
“These Ghanaian hospitals were not full-fledged government hospitals,” he says. “One was an initiative between the Swedish government and the Ghanaian government, bringing in some private investors. The hospitals where our presidents get treated abroad and all our public office holders run to with taxpayers’ money are not government hospitals. Most of them are private hospitals. So, why can’t we attract that level of investment here?”
The long-term solution to the cancer challenge, he is certain, is Universal Health Coverage (UHC), a mandatory health insurance for all Nigerians, enabling them to access the highest possible quality of healthcare without financial difficulty. He says the country’s decision-makers know this but the political will is lacking.
“That ‘without financial difficulty’ is a keyword. The health sector needs much more money than government currently allocates to it,” he says.
“With the UHC, everyone contributes to a medical fund. Everybody can’t get sick at the same time, therefore people with cancer can get treatment and don’t have to pay out of pocket; and if they have to, it will be something the person can afford.
“It doesn’t mean it has to be entirely free. But it has to be that no matter the level where the person operates, a patient will be able to afford healthcare. He doesn’t need to go bankrupt. You will not need to choose between feeding your family and paying for his health, or paying your child’s school fees and paying for your health. The opportunity cost will not need to be anything that is important to you. So it’s just like you want to buy coke — you know, that level — and you will not feel it. That’s the destination
“And it’s something that, if there’s political will to get it done, within two to three years, we can have it. We may say there is no money, but there is money for things that government considers important. If they don’t have money, they’d borrow to fund it. So, all the solution to this is for the government, at federal and state levels, to consider cancer as an important challenge.”
‘SOMEDAY IN THE FUTURE, WE’LL PAY FOR IT’
Would there be consequences if government continues ignoring the underwhelming quality of care available to cancer patients? Chidiebe says yes.
“It means people will continue to die unnecessarily, avoidably,” he says. “And you know the saddest thing? Most people who develop cancer are the aged whom we need to mentor the young ones. We’re raising a generation of youth lacking in mentoring by elders; and someday in the future, we will surely pay for it.”
The Academic Staff Union of Universities (ASUU) says the administration of President Muhammadu Buhari is only preparing the country for a greater future doom with the poor funding of education in the last two years.
“While each senator is paid N13.5million as running cost per month, the same Senate appropriated a paltry sum of N66million for capital projects for University of Ibadan with students’ population of about 30,000,” said Deji Omole, Chairman of ASUU, University of Ibadan branch, on Monday.
He lamented that education funding is at its lowest under the Buhari-led administration, noting that the stifling of education funding under the administration is preparing the country for a greater future doom.
Omole said the nonchalant attitude of the Federal Government to education seems to be the worst in the country’s history, with only about seven percent allocation.
“It will be difficult to have a citizen that will love the country in the future if the current trend of abandoning the poor while taking care of the rich continues,” he warned.
“This can only happen where the ruling class lacks vision like Nigeria. This same government refuses to drop a kobo for the revitalization of public universities.”
The ASUU Chairman also noted that the failure to allocate enough money to public institutions is already causing a gradual crisis of confrontation between students and their respective administrations in some parts of the country.
“Now, many children of the masses are denied access because universities cannot admit beyond what the dilapidated infrastructure can take. Yet their parents cannot afford private university.
“The Federal Government owes about N800billion revitalization funds to public varsities as contained in the agreements with ASUU.”
Omole vowed that the union would resist any plan to force children of the masses out of school by imposing on them dues that are Federal Government responsibilities just as he reiterated that the ruling APC has performed poorly in education.
He said that the President has continued to pay lip service to public education while pacifying militants and terrorists.
The ASUU chairman stated that the masses continue to groan in hardship, while the political class continues to increase their number and pile up enough money taken from the collective patrimony ahead of the 2019 general elections.
In 2016, N480bn was budgeted for education, representing 7.05 percent of the total budget, which was N6.8trn. In 2017, N550bn was allocated to education, representing 7.40 percent of the total budget, which was N7.4trn; while in 2018, the government proposed N605bn for the education sector out of the N8.6trn, the total proposed budget for the year. It represents 7.03 percent of the total
President Muhammadu Buhari says it was a mistake for Nigeria to have stopped the teaching of history in secondary schools, as “people ought to know how they arrived where they are, if they would move forward”.
Garba Shehu, Special Assistant to the President on Media and Publicity, quoted Buhari as saying this during his meeting on Monday with Theresa May, Prime Minister of Britain.
He was reminiscing on the long history of cordial relations between Nigeria and Britain, which have lasted several years “even when we fought a civil war”.
Buhari appreciated British companies such as Unilever and Cadbury “who have stood with Nigeria through thick and thin”.
“But like Oliver Twist, we ask for more investments. We are encouraging more British companies to come to Nigeria,” Buhari told May.
“We appreciate the support you have given in training and equipping our military, particularly in the war against insurgency, but we want to also continue to work with you on trade and investment.
“I am very pleased with the successes in agriculture. We have cut rice importation by about 90%, made lots of savings of foreign exchange, and generated employment.
“People had rushed to the cities to get oil money, at the expense of farming. But luckily, they are now going back to the farms. Even professionals are going back to the land. We are making steady progress on the road to food security.”
Buhari also pleaded with Britain to support Nigeria’s plea to the United Nations for the Lake Chad Basin, which is fast drying up as a result of climate change, to be recharged with water from the Congo Basin.
According to him, this would ensure that residents of Niger, Cameroun, Chad and Nigeria, no longer continue to flee to Europe, via Libya, as a result of the harsh conditions of living close to the Lake Chad, will stay.
“The Lake Chad is now about 10% of its original size, and it is perhaps one of the reasons our youths dare both the Sahara Desert and the Mediterranean, to get to Europe,” Buhari said.
“But if there is inter-basin water transfer, about 40 million people in Nigeria, Niger, Cameroon, Chad, and other countries stand to benefit. I made the case during the Climate Change Summit in France.
“If Lake Chad is recharged, it will reduce the number of youths coming to Europe to increase social problems. We brought back about 4,000 people from Libya recently. Almost all of them were below 30, and Libya was not their final destination. They were headed to Europe.”
Buhari reassured Theresa May that he was more focused on ensuring economic and security stability in Nigeria than on winning a second term in the 2019 general election.
“We campaigned on three major issues, to secure the country, revive the economy and fight corruption. We have elections next year, politicians are already preoccupied with the polls, but I am bothered more about security and the economy,” he said.
Professor Ajanlekoko: Ha! Professor Dick, There’s fire on the mountain! I drove past Awo Hall just now and I saw highly charged students clutching cudgels, ready for mass protest. They’re calling for the head of Professor Dauda! This thing is getting out of hand! Ha! And I always warned Dauda that girls with crazy curvatures are volatile. That’s why I go for pregnant and married students only! How do we clear this mess now?
Professor Dick: The situation is unfortunate. As for me, I only go for the willing ones; many of the girls out there are brainless and poor, so they’re gladly ready to roll in the hay with you. God will take control, sha. I’ve told Prof Amu to use his contacts and appeal to the students. Hasn’t Amu got across to the students?
Prof Shoki: You can’t fully trust anybody in this matter! Some lecturers are happy that this is happening to Dauda, a leading figure in our camp…as if they too don’t eat biscuit bone.
(Dick cuts in sharply): Stop calling Prof Richie, Dauda! Call him by his real name! Dauda the Sexy Guy was only a nickname he got about 25 years ago when he impregnated his secretary and her three daughters. The woman pursued him to his Ikire home, stripped naked and cursed him. I suspect Prof Jack, Prof Sting and co are the ones pushing this girl.
Ajanlekoko: I suggest we continue to refer to him as Prof Dauda because we don’t even know if this office is bugged or not. As an expert in law, I know what I’m talking about. Let’s not call him by his real name, let’s continue to call him Dauda.
Shoki: Ok, I get your point, Ajanlekoko. Let’s stick to Dauda then. Has anybody spoken to him? I’ve been trying to get him since the news went viral this morning. His phone is switched off. I can’t imagine how’s going to face his wife, children and his church, where he’s the second-in-command to the bishop.
Dick: Let’s forget about the family matter for now! Let’s address this immediate crisis! I’ve been inundated with calls from the media, the police, the NDLEA…
Shoki: NDLEA? Why is the NDLEA looking for him?
Dick: They said they want to test him for hard drugs.
Shoki: Hard drugs? Why?
Dick: Because he said he was going to play five matches and potentially score 25 goals.
Shoki: I don’t understand.
Dick: But you listened to the audio now. Didn’t you hear him say he was going to play five solid matches? Knowing him for his killer instinct in front of goal, he would find the net five times during each match, and that makes a tally of 25 goals!
Shoki: Jeez! How could Dauda implicate himself like this? Even Messi and Ronaldo combined aren’t that deadly. This is what I’ve always said; how could you demand five matches for just seven marks? The foolish girl scored 33 marks and he said he was only going to give her seven more marks to make a pass mark of 40. So, why demand five matches? He should’ve played a friendly match and moved on. How can you play European Championship League in only one stadium? I guess that was why the girl refuse.”
Ajanlekoko: Can you believe I was eyeing this little girl, too? Her name is Eni. It’s God that saved me o. Is this how this final year student would have dabarued my life as she’s dabaruing Dauda’s life at 62 years of age? Can you imagine that this wayward girl admitted in the audio that she has a boyfriend? Is that what her parents sent her to school to do?
Dick: Do you want to hear the truth, comrades? Dauda should’ve known the mad girl was setting him up when she was mentioning his name repeatedly. Me, I don’t talk to any of my takeaways on the phone. I use a dedicated email. If any problem arises, I’ll deny. That’s how I escaped when that busty girl, Cossy, wrote the university Senate, alleging that I was demanding sex from her. Nothing came out of the senate inquiry! I just got some boys to subtly threaten her while I engage some girls to give her money. She never showed up at the senate inquiry!
Shoki: Really? You’re lucky. (Please, let me pick this call) Hello, who’s this? Ehn?! Who? Ha! Dauda! But this isn’t your number? Where’re you…? In your driver’s house? Where’s that in Ife? Moore? We’re at our off-campus secretariat in Moore, too. Text the address to me and I’ll come and fetch you immediately. Don’t leave the house o. Students are looking for you. I’ll be there in five minutes… Comrades, let me go and pick Dauda, he’s down the road.
Ajanlekoko: Ok. Please, be careful on the way; those students are very angry. (Shoki exits)
Dick: After this heat, Dauda should just retire.
Ajanlekoko: But he has eight more years to retirement?
Dick: His rod and staff need a rest. He should use the remaining years of his life to beg God for forgiveness.
(Knock)
Ajanlekoko: I think they’re back. Please, open the door for them.
(The office suddenly becomes agitated as Dauda sneaks in disguised like a woman. He removes his wig, blouse, bra, skirt, earrings, goggles and lipstick)
(Sweating, Dauda clears his throat) “Thank you, my people. The enemies will fail in Jesus name…”
Lecturers: “Amen!”
Dauda: I fled the campus barefooted this early morning after listening to the evil audio. I changed my line when calls and texts messages nearly ran me mad. My wife and daughters have been calling me all day. One of my three pets in the church choir texted, calling me a wicked man; she said I was destroying other people’s daughters while I ensured my daughters got married as virgins. My Lord Bishop has been calling, too.
(More of his colleagues offer words of sympathy)
Shoki: As a professor of law, let me give a legal perspective to the audio recording.
Dauda: Please, do.
Shoki: Ok. To start with, you must deny that you ever spoke to that girl. When going to appear before the senate, take along with you one or two Indian films wherein the actors spoke Yoruba. You’ll play the film before the senate, and show that if technology could make Indians speak Yoruba, technology could make your enemies speak in your voice. Comrades, we have to destroy the audio evidence with legal technicalities.
Dauda: What if she comes up with fresh evidence?
Shoki: That’s why we should appeal to the emotions of her parents; that they shouldn’t allow her kill your career. We should beg them with real money. We’ll appeal to them to pressure her not to appear before the senate panel. If she doesn’t appear, you’re in the clear. You’re lucky the Federal Government is busy with re-election now.
Dauda: What if she refuses?
Shoki: Then, you’ll need to go to Jebako.
Dauda: What for?
Shoki: To see Baba Kokonsari Iponri Iku, the great juju man! He’ll cage the senseless girl.
Dauda: But many people know me in Jebako, I can’t go there to do juju again. May be I should call the girl?
Ajanlekoko: Oh! Ok, call her.
(Dauda prostates on the floor) “I hope she picks my call. (Pause) It’s ringing…God, let her pick it …Ah! Aunty Eni, bawo ni, ma? Ma, it’s me, Prof. Em, em, I’m begging you ni, ma. I’m flat on the floor, ma!… Ha! She’s cut the line! Aye mi, t’emi bami!
Tunde Odesola can be reached via: tundeodes2003@yahoo.com
Another demonstration by members of the Islamic Movement of Nigeria (IMN) turned violent in Abuja on Thursday, following failed attempts by the Nigeria Police and Civil Defence Corps to quell it.
A footage made available by a Facebook user shows an Armoured Personnel Carrier (APC) firing bullets and teargas canisters to disperse the protesters, who in turn pelted the APC with stones and other objects.
Following the announcement of a ban on rallies and protests at the Unity Fountain, Wuse, on Friday, the police prevented Shi’ia protesters from gaining access to the garden. The protesters, however, stood their ground, leading the police to shoot sporadically into the air.
One of the protesters was said to have been shot dead during the clash. A witness said he was gunned down while trying to access to the Unity Fountain alongside other members of the sect.
Also, one of the bullets fired by the officers pierced through the window of an office at the Nigerian Communication Commission (NCC) headquarters.
Members of the Shi’ia group have staged a series of demonstrations to protest the continued detention of Ibrahim El-Zakzaky, their leader, who has been in detention since December 2015. Earlier, in January, the FCT Police Command arrested 52 suspects over violent conduct during a Shiite protest in Abuja.
El-Zakzaky was arrested in 2015 following a clash between members of his movement and Nigerian Army. Hundreds of his supporters were killed in the clash and he has, since then, remained in detention despite court orders ordering his release.
Russian investigative journalist, Maksim Borodin of Yekaterinburg, has died of injuries sustained on April 12 when he fell from the window of his fifth-floor apartment.
According to Radio Free Europe/Radio Liberty, Borodin, 32, died on Sunday in a hospital without recovering consciousness. Officially, his death was being investigated as a suicide. However, his editor suspects more.
A Sverdlovsk Oblast police spokesman said it was “unlikely that this story is of a criminal nature”.
He said the door to Borodin’s apartment was locked from the inside and there was no sign of forced entry. He added that the keys to the apartment were found inside and no suicide note had been found.
Polina Rumyantseva, Editor-in-Chief of Novy Den, where Borodin worked, said the same day that she did not believe Borodin committed suicide.
Vyacheslav Bashkov, a friend of Borodin’s, wrote on Facebook on Monday that Borodin contacted him at 5 a.m. on Wednesday to say his building was surrounded by “security forces” wearing camouflage and face masks.
He said that Borodin was alarmed but not hysterical or drunk. Borodin reportedly said he believed his apartment was about to be searched and that the security officers were waiting for a court order. He asked Bashkov to find him a lawyer.
An hour later, however, he called back and said he had been mistaken and that the security officers were conducting some sort of drill.
“I didn’t call him after that,” Bashkov wrote, “although I was waiting for him to write something on Facebook. But he didn’t write anything and on the 13th the media reported that Maksim had been found under his balcony and he was in the emergency room.”
Borodin regularly wrote on crime and corruption. In recent weeks, he wrote extensively about the deaths in February of Russian mercenaries fighting in Syria, identifying several fighters from the Urals city of Asbest who had been killed.
On February 7, a group of Russian mercenaries with tanks and artillery attacked territory held by US-backed opponents of the government of Syrian President Bashar al-Assad.
The US-led international coalition responded with air strikes that are believed to have killed dozens of Russian fighters.
According to some media reports, more than 200 Russian mercenaries died in the incident, although the Russian government has not confirmed the casualty toll.