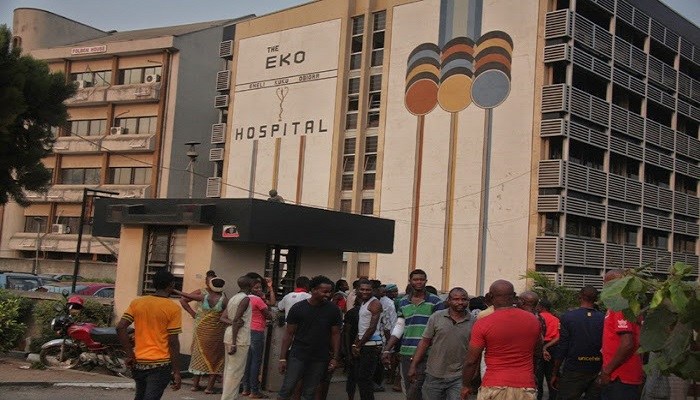“E can’t work, e no fit work,” he said repeatedly, almost reflexively. “I hear it, e can’t work,” he added, again in pidgin English.
Those were the words of Idowu Agunbiade, a local taxi driver in the Federal Capital Territory (FCT, after he was asked about the recent directive by the Federal Capital Territory Administration (FCTA) that all commercial vehicles in the city must be air-conditioned by October.
Making the announcement, Kayode Opeifa, FCTA’s Executive Secretary for Transportation, had said the vehicles “must be registered in Abuja and must carry FCT number plate”.
The ICIR took to the streets of Abuja to find out what the taxi drivers think of the plan.
‘THEY ARE ONLY INTERESTED IN MAKING MONEY FROM US’
As soon as Idowu Agunbiade, a taxi driver, was told about new policy, he cut in that “it cannot work” — because “not every taxi enters estates, banks and ministries, where passengers can afford to pay more”.
“The only way it can work is if they provide more vehicles and give them to drivers at subsidised prices and then they pay in installments,” he said. “But this one they are proposing cannot work. Many governments have done it and failed.”
Asked the last time such demands were made, he said it was during the Nasir El-Rufai administration under the Olusegun Obasanjo presidency. “That’s when they introduced all these buses they now call ‘El-Rufai buses.'”
On the compulsory registration of number plates in Abuja, Idowu again said: “e no fit work”, more emphatically this time.
“The reason is that many of vehicles used here in Abuja are bought from other states, and the dealers buy them in bulk. If the dealer buys like 12 vehicles or six, he will just register them in the state, bring to Abuja and sell to the people.
“Do you expect people who have registered in other states to register again for FCT numbers, spending all over again?”
“Look at this number,” he said, pointing at a passing vehicle. “You see it was registered in Epe. Do you expect someone who obtained this number in Lagos to remove it and get another one here in Abuja? It can’t work! They’ve done more than that. They just want to chop our money again. I’m telling you the reality … for someone like me, it is nonsense. Na lie, it can’t work.”
‘IT MAKES NO SENSE’
Just before the entrance of the expansive premises housing the Ministry of Agriculture and Rural Development and the FCDA is the FCDA Park overseeing Area 1, 10, and 11, Wuse.
“Of course, we’ve heard it,” Fisayo Arojojoye, Secretary of the park association, said. “I don’t think it can be possible because we are not equal. I even heard they said the number plate must be Abuja colour. It can’t be possible. It means all these transporters coming from other states to Abuja with their plate numbers will have to change their plate numbers.
“It can’t be possible. We’re just suffering ourselves in the country. There are some people who are organising to spoil the work of the transporters; that is it. Even the situation we are facing in the county is not okay. Most of us are graduates doing transport work. Does it make sense? It doesn’t make sense at all.”
He also said some couples had divorced because of the insufficiency of income from commercial driving.
“Many Nigerians are now into kabukabu because of the situation,” he lamented. “You cannot afford it again. How can a family man come outside without making any money? Some families have now separated. It’s not done. We cannot be suffering like this, you know, without making anything. It’s unfair.”
A makeshift car park at Jabi, Abuja
‘LET THE GOVERNMENT LEAD BY EXAMPLE’
Joseph Adoyi, who has worked as a driver in Abuja for more than 12 years, gave one basic advice to the government: ‘lead by example’. He said since his arrival, the government had introduced SURE-P, 306 operated by the Abuja Leasing Company and many other taxi schemes.
“Many of those taxis that the government has brought themselves, they didn’t work. They usually got damaged before six months. The car o, not to talk of the AC o!
“That’s why I said they should first lead by example. If they can operate any taxi scheme for at least two years and the AC remains intact, then we can follow suit. You shouldn’t be telling others to do what you cannot pull off. It’s not going to work. They should be realistic.”
When asked about the policy on number plates, he said that it is understandable “because a person cannot be working at Berger and be collecting salary at Dantata”. “It is a way of generating revenue,” he added. But his colleagues soon rose against his opinion.
“With a licensed vehicle plate, you can work anywhere as far as Nigeria is concerned,” an older driver who approached the gathering from behind said passionately.
“They can make their policy,” Joseph insisted. But the older driver maintained that “there are policies that cannot work”.
“No company is producing these plates. It is still the same Federal Government that is giving them out through Road Safety [FRSC],” another driver chipped in. “Okay, if I want to travel to another state, will I go and look for another number?” he asked.
“And all those Abuja AC, is it everybody that can afford to pay the money?” the same driver throws a second question. “Only common N150, people said they cannot pay. They complained and that is why we started carrying four passengers in the back seat. It used to be three. If you add AC to the cars, who can afford it? How much are they even paying the government workers who board our motors?”
“This government is fk up government o. Fk up government. F**k up government,” a driver who sat at the rear left said, the handwriting of frustration legibly gracing his face. “They themselves, can they maintain AC taxis for more than three months?”
“El-Rufai tried it between 2003 and 2006, he failed. London taxi, it didn’t work,” recounted the elderly driver. “Abuja leasing taxi, the 306, it didn’t work. Then, what do they call it, Hyundai, another government scheme, it didn’t work. Remember there was tata, it didn’t work. Then Chevrolet, it didn’t work. What is all this? The thing is that if they want to make policies regarding transport, they should go to people on the streets.”
“People dey hunger, you say AC motor. Na AC remain?” another driver interjected while others laughed ― apparently at the government not the questioner. “Excuse me, people dey hunger, dey die on the road. Even for private cars, how many of them are using AC?”
“Even if it’s working, how many of them put them on? Those government staff bus, in how many of them are the ACs working?” someone added. “If you want to pursue us, then we’ll go. We’ll go back to our villages. They even want me to come back, so I don get opportunity. I’ll find my level.”
“My brother, tell them to order food,” one driver said, with strong emphasis on the last word. “We need food. Food! Let them bring food; you see the way Nigerian people have got very lean and haggard. Is it AC cars that’ll solve Nigeria’s problems? Go and build factories. Use the money to open companies and employ people.”
“Last week, I carried one woman,” one of them narrated. “She said she is a nurse. It’s been more than 15 years now that she’s been looking for job. You say nah AC car nah hin remain. Fifteen years! She’s been carrying files, walking up and down. Tell them, the money they’ll use to order all those yeye motor, let them go and open factories with it.”
An Abuja taxi with a number plate registered in Lagos
‘TAXI DRIVERS ARE TREATED LIKE SMUGGLERS; WE ARE NOT SAFE’
At Wuse Park, the reporter met Ifeanyi Eze who has been in the Abuja transport business since 1998. Ifeanyi also thinks the plan is not possible. “Nobody likes to suffer,” he admitted. “But all hands are not equal.” He also recounted a recent incident of police brutality involving his brother, a fellow taxi driver.
“For taxi drivers, they do not even allow us to have designated parks. Whenever you stop to carry passengers, the same people formed the Joint Task Force to arrest drivers. Is it not inevitable for drivers to stop to get a passenger? And when he wants to alight, you will also have to stop. But they do not give us this freedom.
“Sometimes they ambush drivers at one-ways. Sometimes they remove their uniforms and disguise as passengers, just to bill drivers. They will ask you to pay N5,000. For the VIO, it is more than N8,000. So all these do not allow us to concentrate as drivers. If not that I have nothing else to do, I would have left this business of taxi driving.
“Sometimes, before you know it, the police will hit their guns on your car and damage it. All these dents you are seeing are as a result of gun damage. Other times, they will scatter the glass. The last incident around here, the person whose head they damaged with a gun was my brother, Odoh Dennis. They used 2×2 to scatter his head and all the glasses on his car. He later managed to survive. Everybody knows about this case. They even detained his car, and he still had to look for money to bail it.
“As we are now, we are not safe. We have to be very cautious, as if we are smuggling contraband goods. We have not even satisfied our stomachs. Don’t you know it is someone who has money that can say he wants to open bank account and be saving money? The money to get that thing is not small, and things are very hard now. Some of these cars do not even have AC at all. How are people expected to raise money to buy another car?”
‘THERE IS A LOT OF INJUSTICE IN ABUJA’
Benjamin Adewale, who hails from Osun State, explained that the car he was driving is not even his; he only borrows to use it in the day while the owner uses it at night. The car’s AC was removed, he said, because it was too expensive to maintain.
“We are all looking for what to eat; some of us even borrow our cars,” he lamented in Yoruba. “Now you are saying we should go and look for air-conditioned cars; where do you want us to find those? Maybe you should just send us back to our hometowns; there is nothing we can do again.”
“Just this morning, as I left my home with no money in my pockets, a policeman broke my glass after a lot of pleading, for a car that is not mine,” he narrated. “It was because I did not give him N100 for stopping to get a passenger. Even me had not seen N1 to eat. He even hit my left arm with his baton; I just thought to myself that God will be his judge. I still do not know how to explain to the owner or get the glass fixed. The money I’m supposed to be gathering gradually for my two children to eat will now go into getting a new glass.”
True to his words, glass smithereens could be seen beneath and in between the front seats. He said the incident happened around Npape. Asked what street the policeman was, he pleaded not to divulge.
“Brother, it was on the street. Please, don’t make me put myself into trouble. This is my only source of income; there is nothing I can do about it again…. There is a lot injustice in this Abuja; they treat us unfairly too much.”
How much do the number plates cost? “They are very expensive,” replied Adewale. “Sometimes, at least N30,000 … God have mercy.”
NURTW Branch 2 Office at Utako Motor Park, Jabi
‘GOOD DEVELOPMENT BUT THE POOR MASSES WILL CRY’
Ibrahim Gajide, Deputy Sate Chairman of the National Union of road Transport Workers (NURTW), revealed that that the policy on number plates is already in force in Lagos.
“We cannot drag with the government,” he submitted. “The only thing is maybe we’ll now look for an adjustment of the time so that we can purchase the vehicles. If the government can assist us, then most of our members will dispose their cars without AC and get new ones at the government price, so they’ll be working and paying. That is what we finalised with the members and we’ll be proposing this to the Transport Secretary.”
Asked if transport fares will remain the same with the proposed arrangement, he replied in the negative.
“No, you know, the charges for a vehicle with AC will not be the same as a vehicle that does not have,” he said. “Charges will be different because the consumption of fuel for a vehicle using AC will not be the same as the one that does not have the AC on. So, automatically, the system will be good, but the poor masses will cry.”
SILENCE FROM THE TRANSPORT SECRETARIAT
When Ifeanyi Ughamadu, PRO of the Transport Secretariat at FCDA secretariat was called, the phone was not answered. A text message requesting a physical appointment was also ignored. When the ICIR visited his office, a request to see the Transport Secretary, Kayode Opeifa, was declined on the grounds of “due process”.
Ovi Omo-Agege, a senator from Delta State who is currently on suspension, on Wednesday led some thugs to seize the mace at the upper chamber.
On 90-legislative-day suspension for daring to say the Electoral Act amendment by the Senate was targeted at President Muhammadu Buhari, the Delta Central senator should ordinarily be unable to gain access to the Senate.
However, he and his men managed to breach the National Assembly security and make away with the brace, sparking confusion in the premises.
Following the development, there was tension as senators went into a closed-door session.
Since the Senate sits for 180 or 181 days in a calendar year, Omo-Agege’s 90-legislative-day suspension translates to six months of shutout from the legislature.
At least 15 more Chibok girls than originally thought are alive, as Boko Haram has “confirmed” to Ahmad Salkida, a journalist who has vast knowledge of the insurgency, that the 15 are being held in cells manned a faction of the group.
This brings the total number of surviving Chibok girls to 30 — 15 more than the number originally reported by Salkida on Saturday, the fourth anniversary of the abduction.
Updating his former report, Salkida said that a Boko Haram leader confirmed his report that 15 of the girls were alive and married, but added that another set of 10 and five respectively, are also alive but are being held by factional cells.
“A leading member of the Jama’atu Ahlis-Sunna Lidda’Awati Wal-Jihad or BH (Boko Haram) has now clarified the earlier information about 15 girls. Indeed, the 15 Chibok girls are available, but known to a particular cell that spoke to me emphatically days leading to the 4th anniversary,” he tweeted on Tuesday.
“However, two other cells within the larger group has brought additional information, clarifying the earlier information, that there is another 10 girls available to another cell. Outside of the 15 and 10, another 5 amongst the girls are also alive as at early hours of today.
“But the set of 5, according to the group today, have apparently become permanently embedded in the doctrines and teaching programs of the Sect and have asked not to be considered amongst those likely be included in any release in the future, if there would be any.
“In BH, you do not know what you don’t have access to because of the segmentation of authority. It’s part of the ethos of criminality to restrict access of lieutenants to critical information. You only know what obtains in the cell you control.”
5/ However, two other cells within the larger group has brought additional information, clarifying the earlier information, that there is another 10 girls available to another cell. Outside of the 15 and 10, another 5 amongst the girls are also alive as at early hours of today.
Salkida reiterated that the terms for a possible release of the girls – “for those that want to be released” – will depend solely on their husbands’ willingness to let them go.
He also expressed disappointment that “the government in its might and given the machinery available to it, peremptorily declared to the public that it lacks institutional memory regarding the processes of the Chibok girls”.
9/ Back to the response of the presidency, it is most disappointing that the government in its might and given the machinery available to it, peremptorily declared to the public that it lacks institutional memory regarding the processes of the #Chibokgirls. pic.twitter.com/BbqoxvVWLK
“Eighty-two girls were killed” amongst hundreds of other hostages that are unheard of, mainly in crossfires and bombardments; “some died long ago, some more recently”; a few are single or ‘widowed’ and it’s unbearable to publish their names here. This is the story of the Chibok girls,” Salkida concluded.
Uche Secondus, National Chairman of the Peoples Democratic Party (PDP), received a total of N250 million in cash in two installments from Sambo Dasuki, former National Security Adviser, in 2015, according to a report by the EFCC.
This is in response to Secondus’ denial that has received any money from Dasuki, neither did he direct anybody to receive money on his behalf.
Secondus’ name featured in the ‘looters list’ released by Lai Mohammed, Minister of Information and Culture, but he has since taken the matter to court, accusing the Federal Government of libel.
But, according to the EFCC report sighted by Punch, “Uche Secondus received N200m in cash from the ONSA (Office of the National Security Adviser) with voucher 0244.
“His Special Adviser, one Chukwurah, signed for the money on his behalf on February 2, 2015. Earlier, he had collected N50m which was personally received by him on November 7, 2014.
“The funds were approved by Col. Sambo Dasuki (retd.) for unknown reasons but were merely referred to as ‘special duties.’”
Also the report said the trio of Secondus, Adamu Mu’azu, former PDP National Chairman and Bassey Akpan, a PDP senator, received cars worth N1.1 billion from Babajide Omokore, an oil billionaire who is also currently standing corruption trial.
Secondus’ share of the car ‘gifts’ included a Range Rover Biography SUV worth N50 million, a Benz G63 worth N36 million, 15 Toyota Hiace mid-roof buses worth N120 million, 10 Toyota Hiace buses worth N90 million, and two Toyota Hilux vehicles worth N14 million.
In all, Secondus received vehicles worth N310 million from Omokore between June 2013 and November 2014.
Mu’azu allegedly took delivery of vehicles worth a total of N504.5 million between May and August 2014, while Akpan received vehicles worth N303 million during his time as Commissioner for Finance in Akwa Ibom State, and later Chairman of the Inter-ministerial Direct Labour Coordinating Committee.
Among the vehicles collected by Akpan were: “a BMW X5 BP worth N50 million; an Infinity QX56BP worth N45 million; a Range Rover worth N40 million; three Toyota Hiace buses worth N27 million; two Toyota Hiace High-roof buses worth N16 million, six Toyota Hilux D cabin vehicles worth N42 million, as well as other vehicles worth N83 million”.
“He (Akpan) has been invited on several occasions but he has refused to show up. He was supposed to come to the EFCC office on Monday (yesterday) but he refused to come,” an unnamed EFCC told reporters.
When contacted, Ike Abonyi, media aide to Secondus, said the matter was already in court and that the Federal Government should present its evidence in court if it has any.
“There’s no need to be talking about a case pending in court in the newspapers,” he said. “If the government has anything to say, they should file it before the court as demanded.”
Social networking platform Twitter experienced intermittent spells of downtime on Tuesday, with users unable to log in for some 45 minutes.
Attempts to access the networking service only led to a page with a waiting notification: “Something is technically wrong.”
The error message further thanked the internet user for “noticing”, with a promise to “fix it up and have things back to normal soon”.
This incident occurred roughly between the hours of 2:50pm and 03:35pm West African Time (WAT).
The website went offline at around 2.50pm, came back online at 2.58pm, then went back offline at 3.01pm. It again came back up at around 3.35pm and has been stable since then.
When the problem was resolved, Twitter itself tweeted about it, saying: “Some users may have experienced problems sending and viewing Tweets earlier today. This issue is now resolved.”
Some users may have experienced problems sending and viewing Tweets earlier today. This issue is now resolved.
The Senate has summoned Godwin Emiefele, Governor of the Central Bank of Nigeria (CBN); Kemi Adeosun, Minister of Finance; and Mansur Dan-Ali, Minister of Defence, to explain the “unlawful withdrawal” of $462 million from the Federation Account.
The summons resulted from a point of order raised by Sam Anyanwu, Chairman of the Senate Committee on Ethics and Privileges, who said the withdrawal was made without legislative approval as required by law.
To back up his motion, Anyawu referred to Section 80 (2) and (3) of the 1999 Constitution, which prohibits the withdrawing of money from the federation’s “consolidated revenue fund or an other public fund” without prior consent of the National Assembly or in the manner prescribed by it.
He submitted that the CBN Governor and the ministers of finance and defence should be summoned for appropriate questioning.
“Mr President, I have it on good authority that in March 2018, a whooping sum of $462 million was withdrawn from the federation account and paid for helicopters to an American firm called Helicopter Tecno Fights Helicopters and this was done without the approval of the Senate,” he said.
“As a citizen, senator of this place, I want to find out how this thing was done and I suggest that we invite the CBN governor, the Ministers of Finance and Defence to tell us how this money was withdrawn and paid to an American companu without the approval of the Senate.”
The Senate then referred the matter to the Committee on Appropriation to summon the trio and investigate the allegation. It also told the committee to submit its report to the house within a week.
This allegation is coming barely two weeks after President Buhari ‘approved’ the release of $1 billion from the Excess Crude Account (ECA) “for the purchase of more equipment for the military”.
Rochas Okorocha, Governor of Imo State, says he has no serious opposition going into the 2019 senatorial election, as he had retired the likes of Arthur Nzeribe and Achike Udenwa, who used to be political heavyweights in Imo State.
Okorocha expressed certainty that Uche Nosu, his son in-law, would win the governorship seat in Imo State, while he would himself clinch a seat in the Senate, after which he will succeed President Muhammadu Buhari in 2023.
“Nwosu will win in 2019,” he said on Tuesday while addressing some politicians who paid him a courtesy visit at the Government House in Owerri, the Imo State capital.
“Don’t be afraid, I am there. I have retired the Arthur Nzeribes, the Udenwas; now I will retire the rest of them finally.
“I know them and they know me; their plan is to push me so that they can get the Senate. It’s a lie; I will run for the Senate as well.
“Nwosu is the least of the political children I have trained but I don’t know any of them as much as I have known him. I took him up when he was just nobody and he grew to the height he is now, his only sin is that he is my son-in-law.”
Expressing delight at Buhari’s decision to seek reelection, Okorocha said: “Buhari will win again and again. After Buhari, the turn will come to South-east and it will be the turn of Okorocha.”
Festus Keyamo, Senior Advocate of Nigeria (SAN) has been appointed Director of Strategic Communications, for President Muhammadu Buhari’s 2019 reelection campaign.
Keyamo made this known via his verified Twitter handle on Tuesday.
“I will be making a formal statement on this much later,” he tweeted.
With this letter below👇, I have just been appointed the Director, Strategic Communications (Official Spokesperson) for the President’s 2019 Presidential Campaigns. I will be making a formal statement on this much later. pic.twitter.com/VxRZcI9Jdo
Keyamo, 48, hails from Ugheli, Delta State, and graduated from Ambrose Ali University, Ekpoma Edo State in 1992. He was called to the Nigerian Bar in 1993 and was elevated to the rank of a senior advocate in 2017.
In his capacity as spokesman for the Buhari reelection, he is expected to ensure that his principal wins the APC presidential ticket and, subsequently, the general election in 2019.
President Muhammadu Buhari apparently considers the huge cut to rice importation from Thailand one of his administration’s greatest achievements. During his ongoing visit to London, he has boasted to Justin Welby, Archbishop of Canterbury, and British Prime Minister Theresa May about Nigeria’s ‘road to food self-sufficiency’.
HIS CLAIMS
According to statements released on Wednesday and on Monday by Femi Adesina, Buhari narrated to the two personalities ― in what appeared almost like memorised speech ― how Nigeria has cut rice importation by 90 percent.
“I am very pleased with the successes in agriculture,” he told Prime Minister May, on Monday. “We have cut rice importation by about 90%, made lots of savings of foreign exchange, and generated employment. People had rushed to the cities to get oil money, at the expense of farming. But luckily, they are now going back to the farms. Even professionals are going back to the land. We are making steady progress on the road to food security.”
This claim by the President is backed by figures released by the Thai Rice Exporters Association, which detail rice exports from Thailand to all countries, including Nigeria, from 2015 to 2017.
In 2015, the Asian country exported 644,131 metric tons (MT) of parboiled rice to Nigeria. In 2016, this figure dropped drastically to 58,260MT. And, in 2017, it fell even more to 23,192MT, resulting in a 96.7% decrease in just two years. This is apparently great news for the country ― except that these figures do not tell the whole story.
FACTS AND FIGURES
Benin Republic has always been another major importer of rice from Thailand. In 2015, Thailand exported 805,765MT of parboiled rice to the West African country. This figure, however, skyrocketed to 1,427,098 in 2016, and 1,811,164 in the year that followed. The same trend can also be noticed regarding Cameroon, another country bordering Nigeria. It imported 449,297MT of rice in 2015, 505,254MT in 2016, and 744,508MT in 2017.
“Nigerians, of course,” Mohammed had himself confessed. “In fact, as Nigeria’s rice import falls, Benin’s rice imports increase. Most of the parboiled rice imported by Benin eventually land in Nigeria through smuggling.”
Even Audu Ogbeh, Nigeria’s Minister of Agriculture and Rural Development, admitted in 2016 that Benin traders imported parboiled rice shipped in from Thailand, “station themselves at our borders and smuggle these items into our economy”.
According to data from the International Grains Council, over half of Nigeria’s imports in 2015 entered from neighbouring Benin, where the duty on rice is only 12%, and most of Benin’s rice imports, up to 30,000 truckloads per year, are routed via transit shipments through Niger to the northwest of Nigeria.
It is also suggested that since Nigeria is the only West African country that exclusively consumes parboiled rice, it is easy to deduce that the 85% share of Benin imports that are parboiled are Nigeria-bound through the orchestrations of clever traders.
THEREFORE…
President Muhammadu Buhari has, therefore, been economic with the truth in his conversations with his English friends. Under his administration, Nigeria may have cut lawful rice importation by more than 90% but unlawful importation is still booming, which clearly means suggestions the country has equally made 90% progress on the path towards agricultural self-sufficiency are completely false!
EDITOR’S NOTE: All the names of cancer patients in the undercover parts of this story have been concealed as a mark of honour for their struggles and respect for their privacy. An undercover method was unavoidable, as it was the only way to ascertain the true quality of healthcare available to them in federal hospitals. The ICIR is in possession of video and audio evidence of ALL the findings of this story.
For a futile month in 2017 and two fruitful ones in 2018, ‘FISAYO SOYOMBO, Editor of the ICIR, was accompanied by a private oncologist in going undercover at two leading teaching hospitals in the country to ascertain the true quality of healthcare available to cancer patients. Together, they discover how the lack of functioning radiotherapy machines is impeding the treatment of numerous cancer patients and aiding the spread of the disease from a point in their bodies to others, leaving many of them stranded midway through their treatment and their families resorting to lobbying hospital officials. This is also a celebration of love — how cancer patients are fighting to see every new day by merely seeking to repay the care and faith and sacrifice of their lovers.
This is one of the most intense, riveting love stories you will ever read. Contrary to what you may be thinking already, it isn’t set in the Hotel President Wilson in Geneva, Switzerland — the world’s most expensive hotel — or in the famous Burj Al Arab in Dubai, the third tallest and fourth largest hotel in the world. It isn’t set in Paris, the fabled ‘city of love and romance’, either. Instead, this true life story is set in the frenetic city of Lagos, specifically domiciled at the gynecology ward of the Lagos University Teaching hospital (LUTH). Dateline, February 2018.
A dark, beautiful young lady from Edo State — confined to the bed by terminal sickness — writhes in agony. She twitches her right fingers but the rest of the arm is static; it’s swollen and bandaged, the source of enormous pain. She closes her eyes and grits her teeth as though mustering all the strength within her in an attempt to say something to the doctor, but she doesn’t. Weak and helpless, she gives up.
Her boyfriend — a dark, handsome, confident young man from Delta State — cut a forlorn picture. The agony in his eyes is palpable; it is clear he wants to help, but he can’t. He can’t even hold her hands in his; one touch and she’d scream in excruciating pains. Instead, he stares at her in consolation, wearing a sombre look suggesting he would rather bear the pains on her behalf.
THE POWER OF LOVE
One of his girlfriend’s breasts has been cut off; mastectomy is what the doctors call it. It is from there that the cancer raging through her body emanated. In all, she has undergone surgery, chemotherapy, radiotherapy — the three commonest medical solutions to cancer — yet her condition is deteriorating. She is becoming paler, losing weight, now unable to move — because the cancer has so spread round her body that she now suffers from metastatic neuro disease. Also, due to the cancer, she has lymphedema, responsible for the swelling of her eyes and right arm. She has intense chest pains and struggles for breath after weeing. She’s on oxygen as well. And what more? Breasts don’t regenerate; that breast is gone forever. Still, he loves her.
“I love her so much. She was my crush then when we were in Uniben but she used to play hard to get,” he says. “I never knew we would meet again in Lagos.” For the first time in a pain-laden 15 minutes, she blushes, her face lightening up and her lips slowly parting to release such glorious smiles that set one wondering just how pretty she must have been in her healthier days. Love, oh love! Such medicine even to the sick.
They have been dating for roughly six months. After losing track of each other back in Benin, where they both grew up, they met fortuitously on the streets of Lagos in January 2017. She had just undergone surgery at the time; and as the friendship blossomed, she told him she had cancer, and that one of her breasts had been removed.
“Trust me, it wasn’t an issue,” he says of the breast removal. “Even she was shocked [by my reaction] when she told me; I never felt anyway. If you love someone you have to accept them the way they are; it’s the truth. Life goes on. You can’t hold on to that, because it’s not her fault that she has cancer. I have accepted it.”
What he has accepted is often not so easy to deal with. As explained by the external oncologist who joined the journalist in entering the hospital undercover, there are ample examples of husbands who divorced their wives after mastectomy, despite already having kids after several years of marriage. In fact, there are cases of husbands who prevented their wives from undergoing the procedure, despite knowing that retaining the breasts literally meant a death sentence.
One more time she clenches her fists in pain and her man’s face contours into a frown. It’s such an unpleasant sight to behold. For how long will they endure this pain? When will she be strong enough to get out of the hospital and return to her normal life?
“I pity her a lot,” says the undercover doctor. “But I pity her boyfriend more. This lady I see has one year — probably two more — to live. The doctors handling her case must have told her, and I hope she has told her man — because no doctor will. The doctor tells the patient the truth but no one else. There is a doctor-patient confidentiality that forbids the doctor from opening up to anyone else other than the patient.”
BLAME CANCER, BUT BLAME THE HEALTH SYSTEM MORE!
When — or if — she dies, her death will be blamed on cancer, but make no mistake: the Nigerian health system would have been hugely complicit. Her death would have been fast-tracked by the many inadequacies of a comatose public health system. Why?
Last year, she was scheduled to undergo external beam radiotherapy (RT) treatment, ideally delivered by a machine called Linear Accelerator, or Linac for short. All linacs generate high energy x-rays (photons), which are then carefully aimed at the area of the patient’s body being treated by the Consultant Oncologist. First, LUTH’s RT machine is not linac, therefore incapable of producing the maximum result. Two, she was scheduled for 18 courses. But after 10 rounds, the RT machine broke down (in June 2017). Thus marked the end of her radiotherapy treatment — just at the halfway mark. Almost one year on, the machine hasn’t been fixed, neither has a new one been bought.
In any case, there is good reason to doubt the efficacy of those 10 sessions, as she recalls the difficulties faced by patients in the final days of the broken-down machine. “There were serious issues with the machine,” she says. “A lot of people were having complications; some were overdosed, others under-dosed.”
A LETHAL PAUSE
According to the undercover oncologist, the aborted procedure she was undergoing is called ‘adjuvant radiotherapy’, that is radiotherapy done following a debulking surgery (also known as tumor removal surgery).
“The courses are spread out in such a way as to target the remnant metastatic tumour cells,” he explains. “She was placed on 18 courses of radio, spread out over months, in order to deal with the problem cell by cell. So, what happened when the radiotherapy machine spoilt is that you stopped the process of clearing the metastatic cells.”
The implication is that those cells that had not been cleared after the 10 courses would continue giving her symptoms manifesting as pains in parts of the body. “Cancer cells feed on blood, so the person will still look sickly,” he says. That is the best scenario for the luckiest patient.
“But the worst — which is usually the case and which has clearly happened in this case — is that the metastasis continues, which means as the cells around her breasts were being targeted, the metastasis could have gone to the lungs and could have even gone as far as the brain — because the process of spread is through the blood or through the lymph nodes,” he adds. “The patient can start coughing blood because the cancer has gotten to the blood, or you start seeing signs of encephalopathy because it has got to the brain. You see she complained about back pains? It is because the cancer has spread to her back. These are all favourable areas for breast cancer spread; breast cancer likes the brain, the lungs, the bones.”
She is clearly a victim of the system. Unlike most patients who report to the hospital late, she sought medical advice once she noticed a lump in her breast in September 2015. After running a series of tests, she was diagnosed with cancer. She promptly began treatment, staying on chemotherapy for six months before going under the knife in February 2017. This was followed by took two courses of chemo after surgery, before enlisting for the botched radiotherapy treatment.
“I didn’t delay treatment at all,” she says emphatically. “Everything was rapid.”
STRUCK DOWN BY INDUSTRIAL STRIKE
She’s not the only victim of the system, though. Of the dozen others whose stories would be touched in this piece, one decides to bare it all. As he explains, there’s nothing left of his human pride. All of it has been “taken away”.
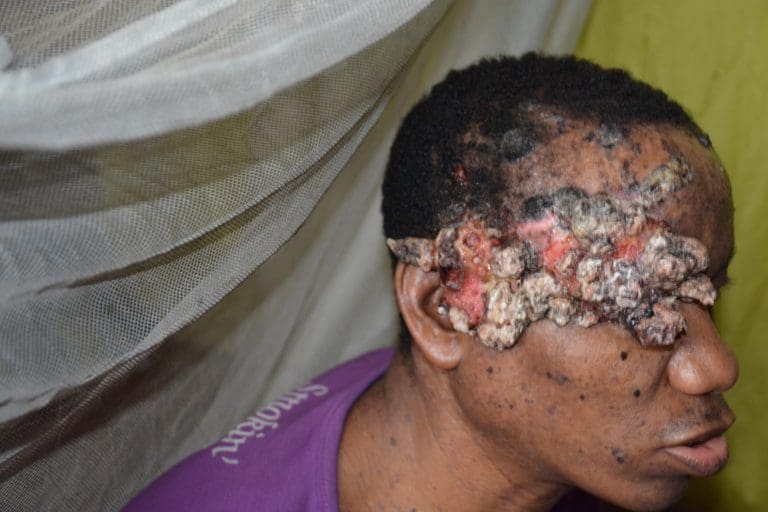
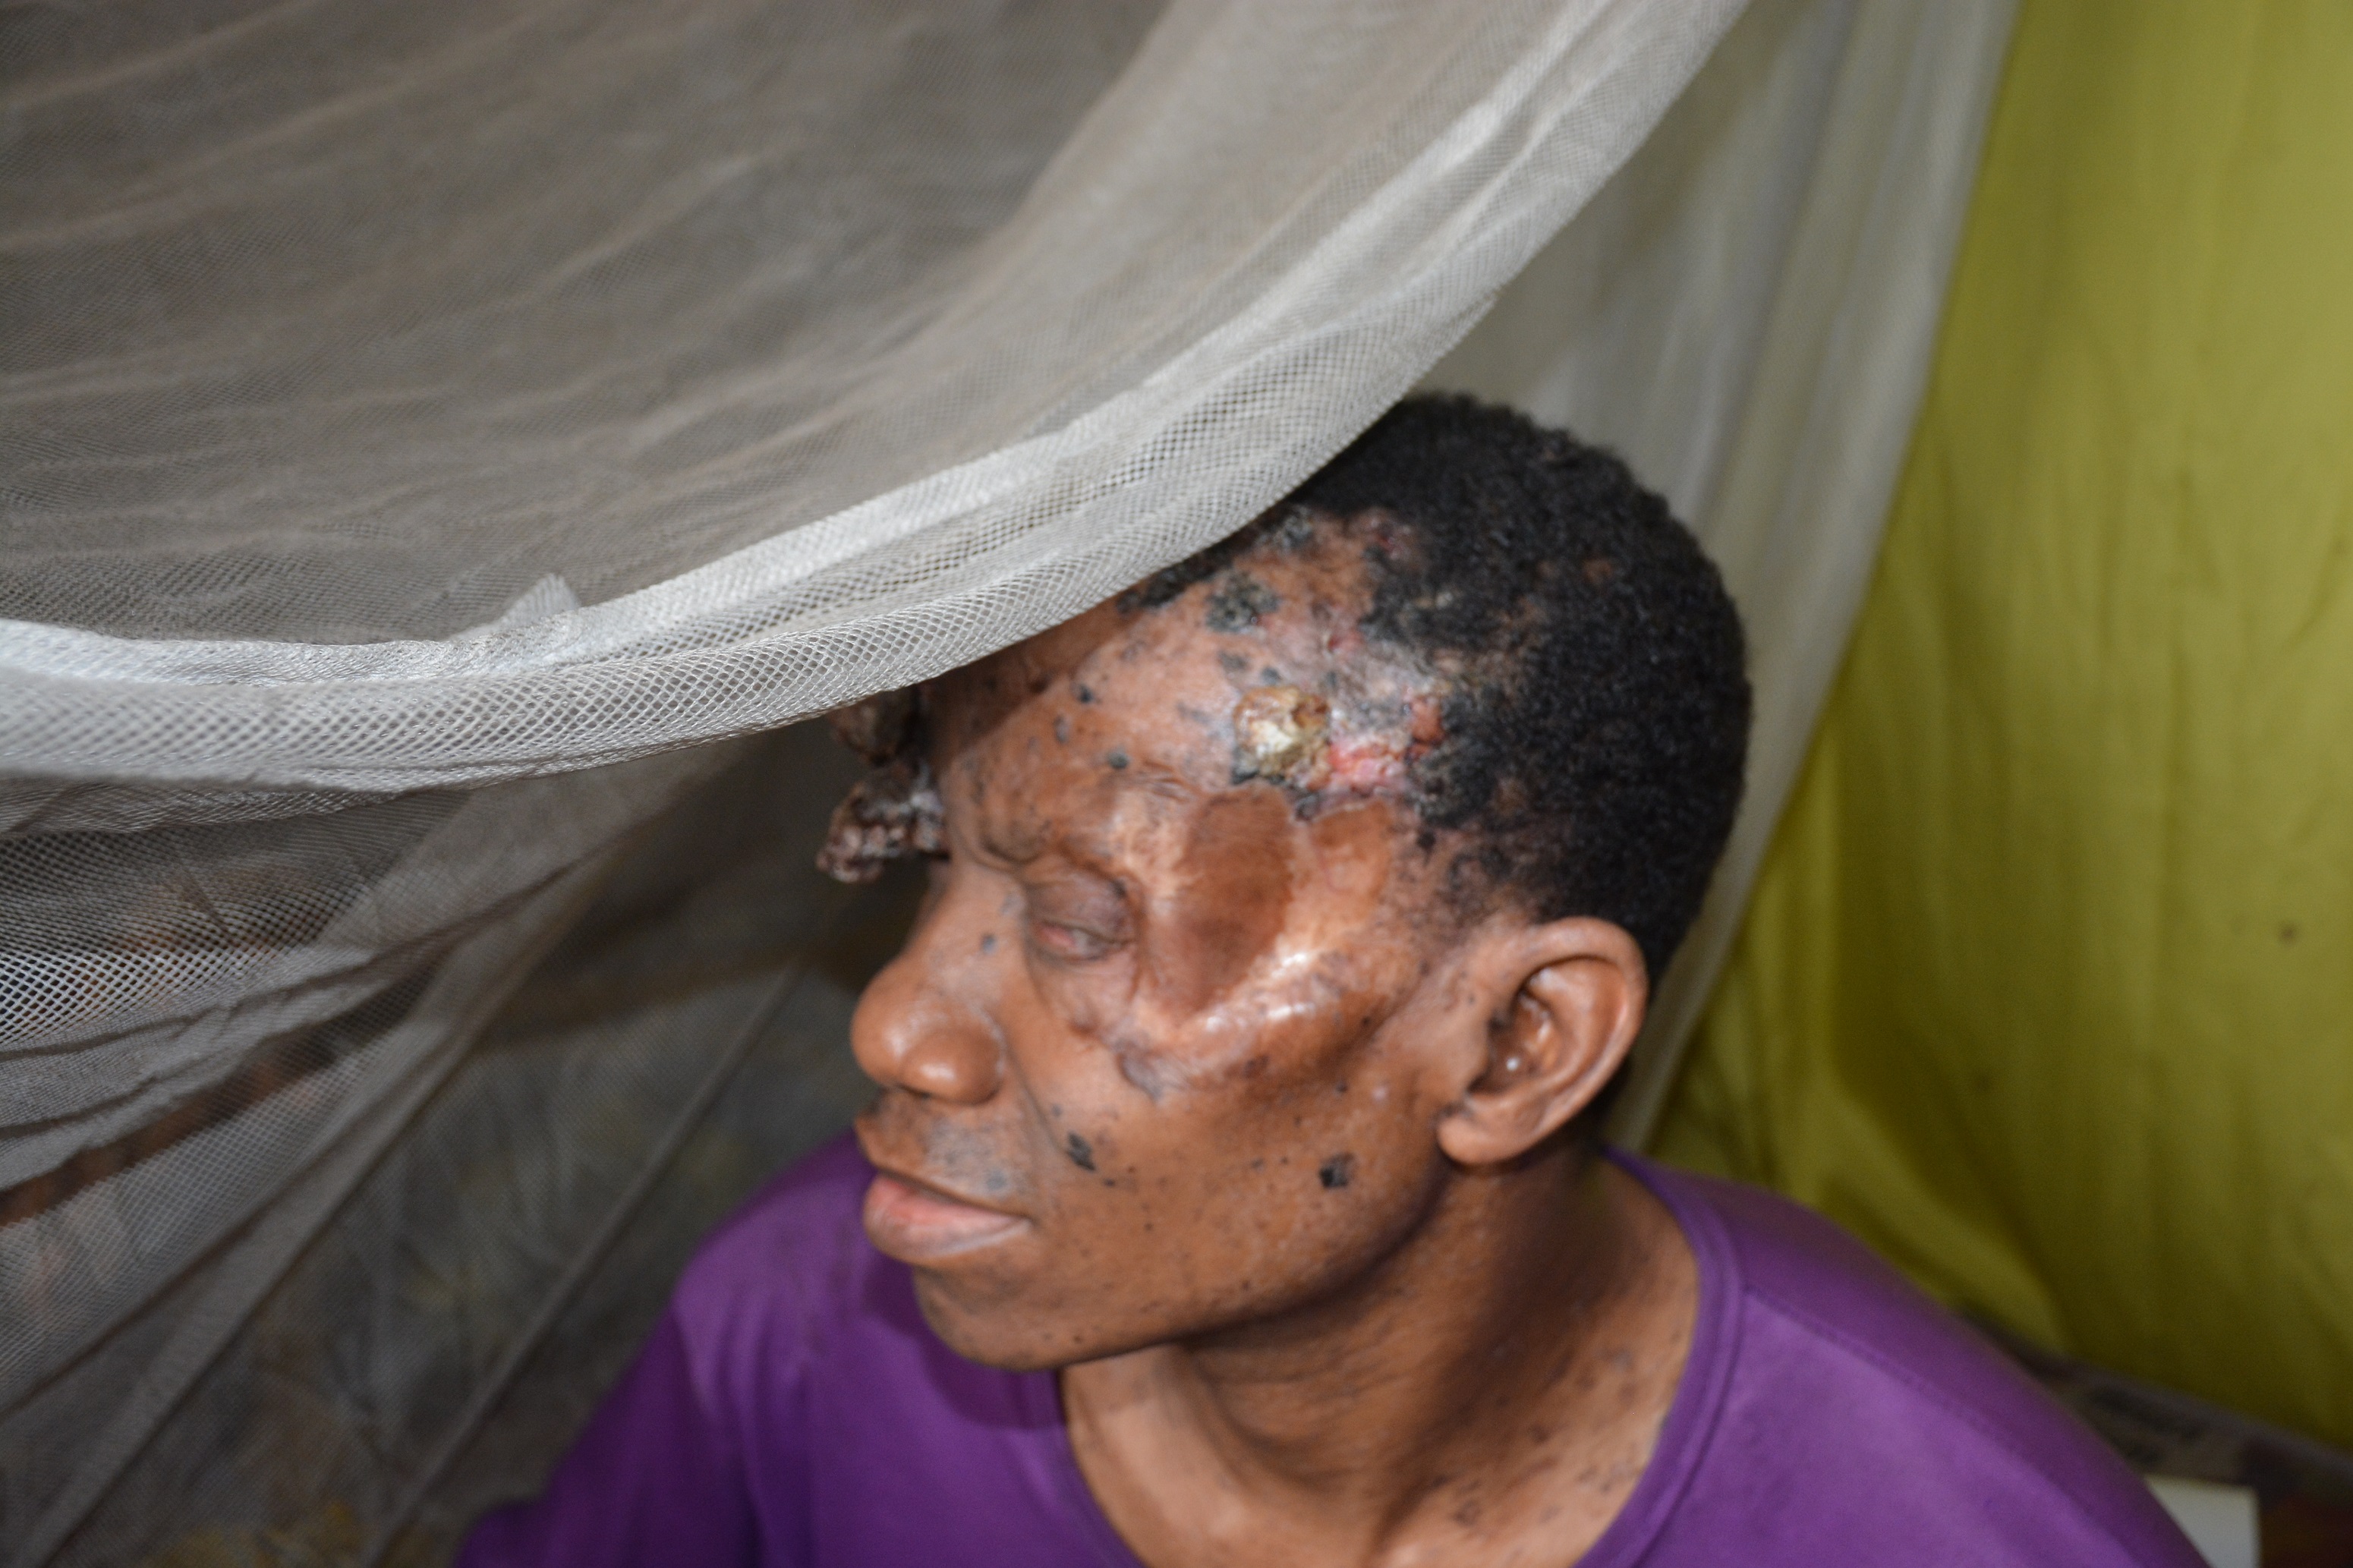
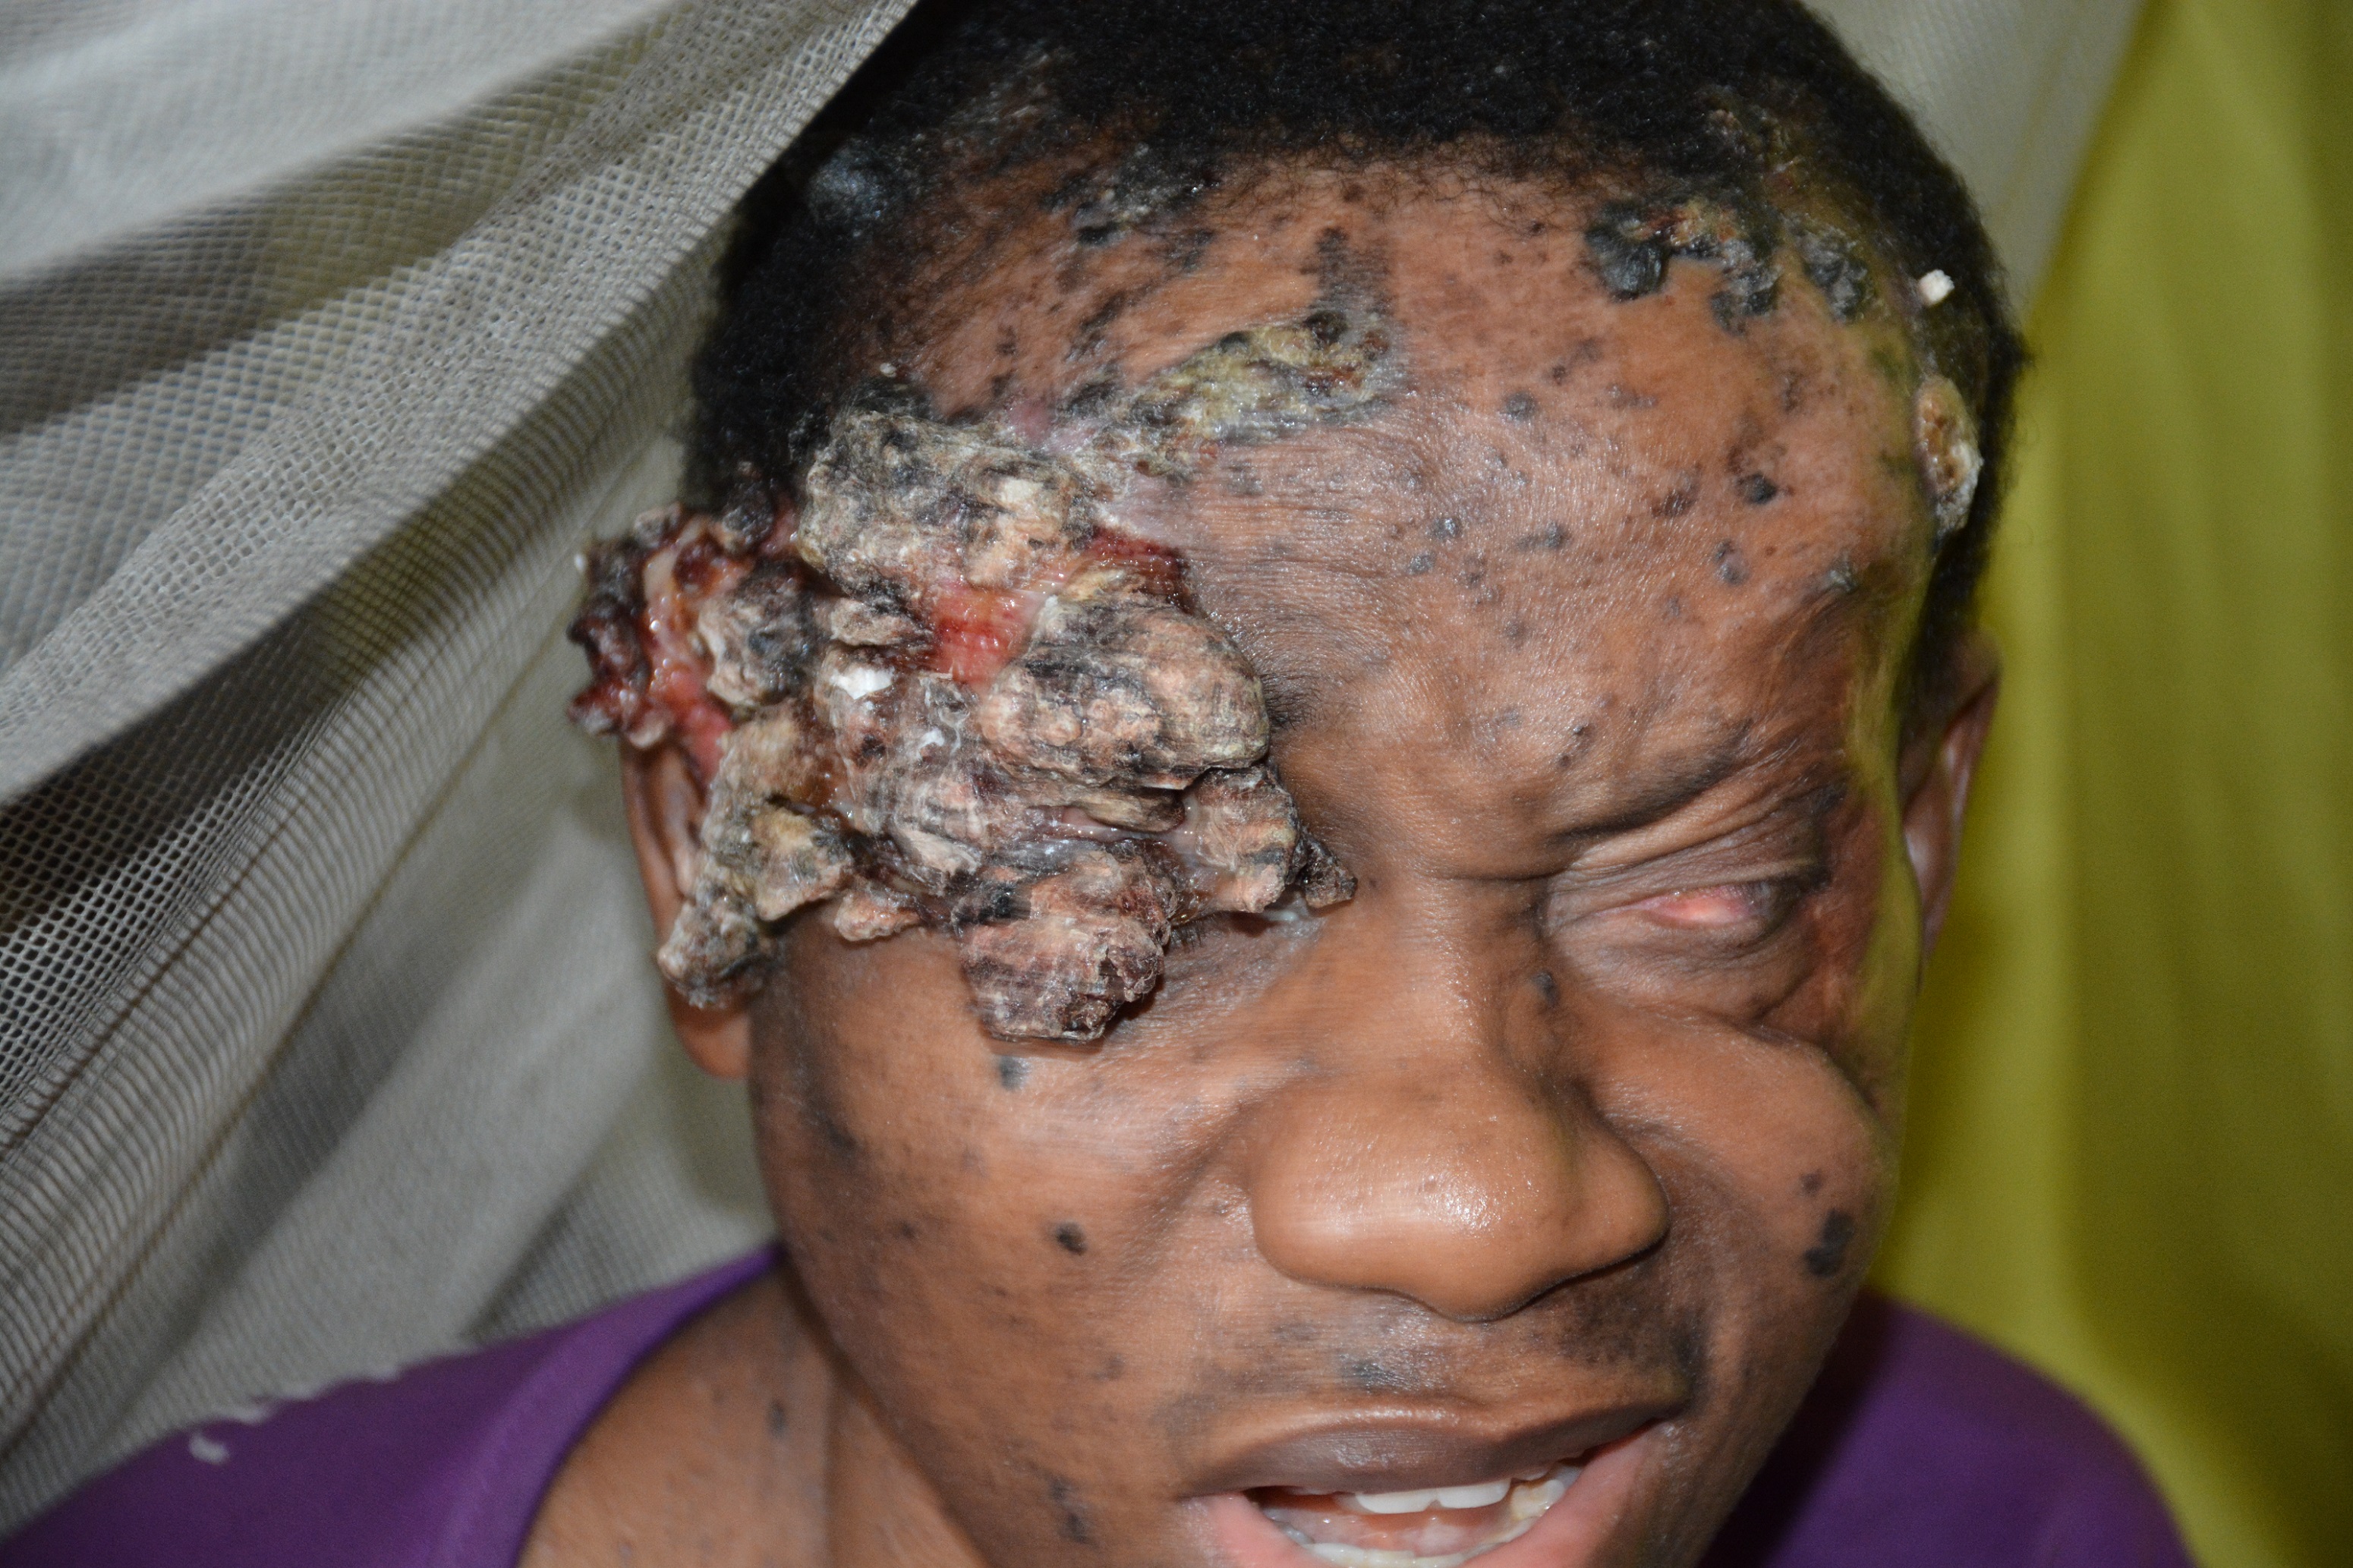
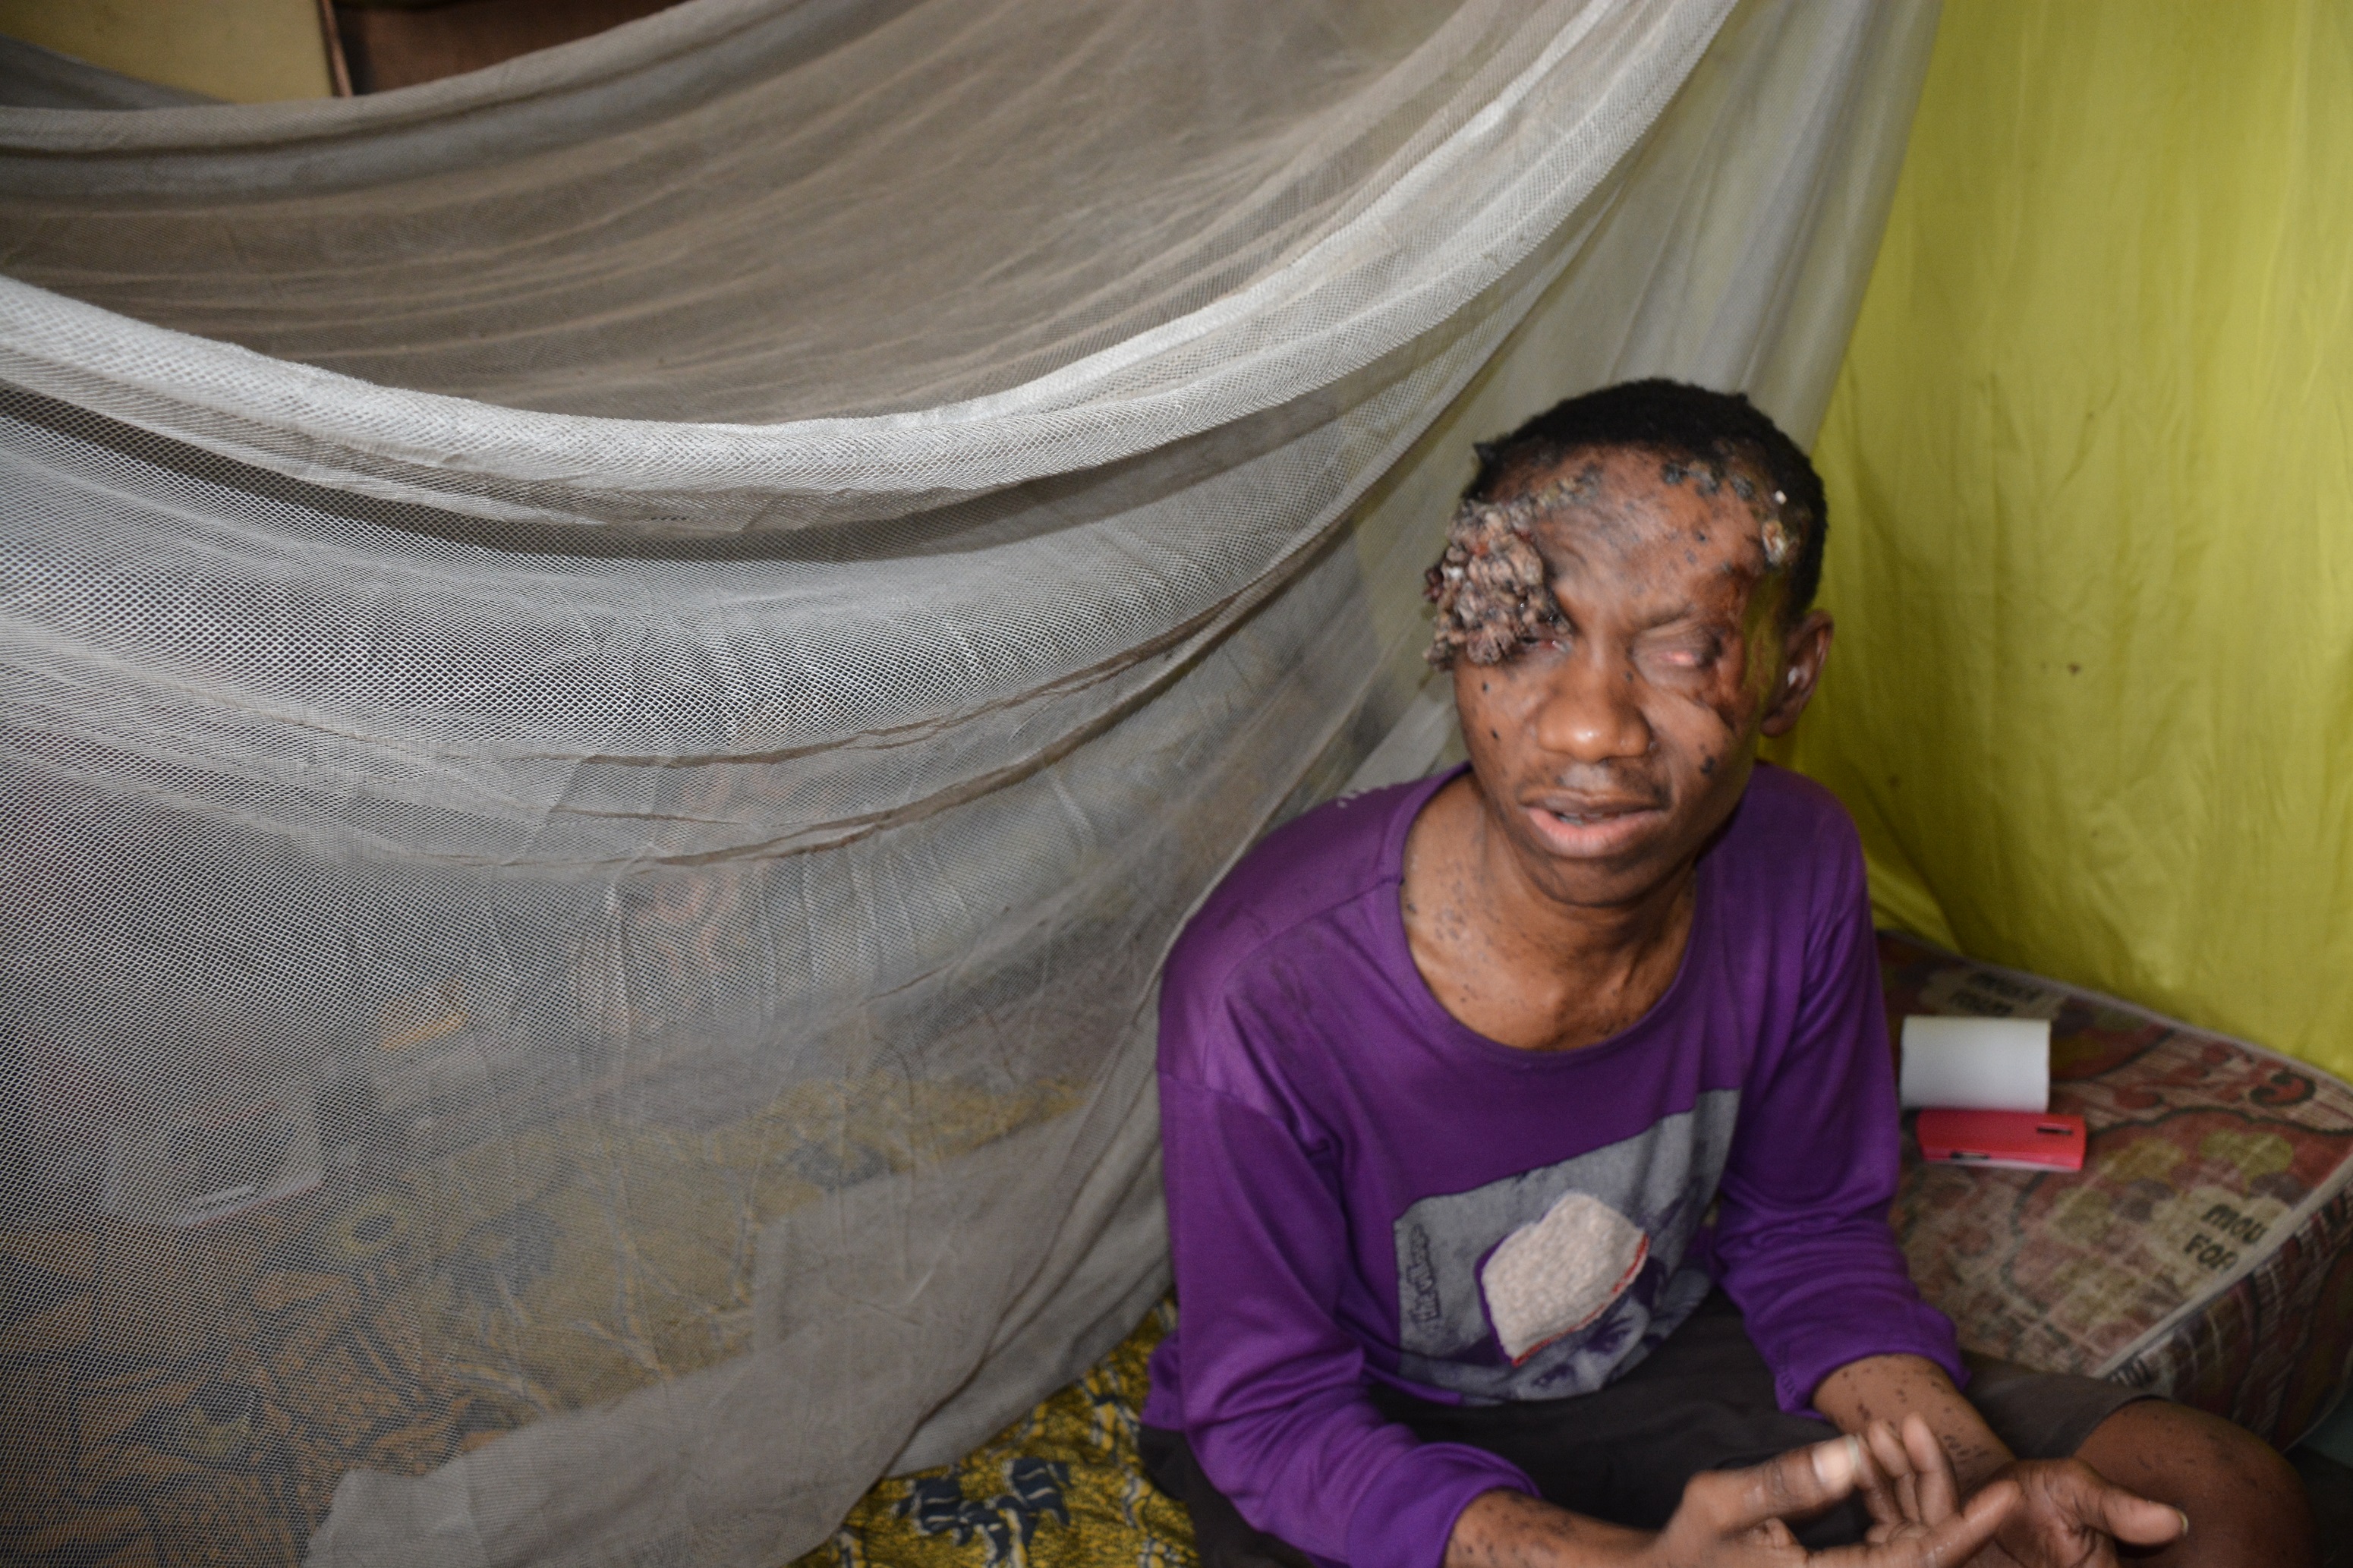
Now 42, Muhammed Musa was only five years old when his parents noticed a small growth around his right eye. It was small but it wouldn’t leave. Best description to give it: “permanent pimple”. As the years passed, it initially didn’t hurt, neither did it rise in bulge. But as Musa approached adolescence, the pimple began to show that it wouldn’t be left out. Then it began to multiply. From the eyelids, similar sights suddenly began appearing on other parts of his body. Rashes! So his mother thought, and thus she sought native treatment in their Village in Edo State.
In his mid-20s — now a man and now in Lagos — Musa sought medical help. Cancer of the eyelids, the doctors said — with attendant tumours that needed to be removed. This was disturbing news because he couldn’t raise the funds. “None of my people had money, as I come from a really poor family,” he recalls.
However, by 2004, he had managed to raise just enough money to remove the tumour. It was a minor surgery. It looked like he had seen the end of his travails. If only he knew that was just the beginning.
Within two years, the tumour was back — this time on the left eye. He had barely recovered from his huge indebtedness courtesy of the 2004 operation. Musa frantically began job-hunting, hoping to be able to save enough to someday fund a second operation. But no one would employ a sick candidate. “That was how I suffered from 2006 till 2010/2011 when I eventually raised the money needed to remove the tumour,” he says.
AN EYE FOR THE SYSTEM
The cancer spread from an eye to another as Musa awaited the end of doctors’ strike actions
Then something heartbreaking happened. The National Association of Resident Doctors (NARD) embarked on a nationwide industrial action, after a series of warning strikes, to “draw the attention of the Federal Government to the deteriorating state of the health sector and low morale of doctors”. As the action coincided with Musa’s surgery date, he missed a big chance. That was in April 2010. Two more industrial actions followed, and on each occasion, the patients were discharged and no one reached out to them upon resumption of work. In all, Musa waited on the doctors for so many months, “almost a year”. Of course, the cancer wasn’t waiting. It spread so rapidly that it cost Musa his eye.
“When I started visiting the hospital, the tumour was quite sizeable, but not so big to the point where it would have affected my eye,” he says in a teary, regretful tone. “But the tumour became overlarge because of the strike action. The doctors would even admit us preparatory to surgery, but there would be strike so they discharged us each time.”
When the last of the industrial action was eventually called off, LUTH didn’t reach out to him. He was “lucky” that the tumour was giving rise to wounds that needed to be dressed, so he went to a private hospital where the wound was dressed for ₦10,500. Subsequent ones were to cost ₦5,000 per session. He didn’t have the ₦5,000 when the second session was due, so he risked an unsolicited visit to LUTH to see if someone could dress the “painful” wounds. “When I got there I met the doctor, and he said they were looking for someone to send to me, that the strike was over and they wanted to perform the surgery. So they gave me a date: March 14, 2011. But the tumour had grown so large that doctors said he would have to lose his eye.
FORTY-TWO AND STILL SINGLE
No wife, no kid at 42. Who will take care of Musa?
Musa eventually went under the knife, sacrificing his right eye for the decay in the system. One more development: his other eye had become badly affected by the wait; so, not long after the surgery, a tumour began developing there as well. In 2013, he was told another surgery would cost him ₦700,000. Unable to afford it, he opted to try the Lagos State University Teaching Hospital (LASUTH), where he didn’t know more bad news awaited him.
“Because the fees they charged was too much, I went to LASUTH at Ikeja. They said there would be consequences if they performed the surgery. One, the second eye would have to go. My ears would stop working. They would remove all the skin on my head, and use another to cover it. That was in 2013,” he explains, tears coursing down his eyes.
“I told them I couldn’t do it — because the left eye had already gone. If I should lose the right one, who will take care of me? Due to this problem, I am still single at 42. I don’t have a wife; I don’t have a child. So who would take care of me?”
‘I’M DYING BUT I DON’T WANT TO DIE’
Musa’s swollen legs
Back then in 2013, Indian doctors told him they could remove the tumour and also save his eyes. But it would cost him N3.8million. but to pay that was someone who couldn’t afford N700,000
By August 2016, the bill had risen to N8.5 million. Without a job, someone to take care of him, or even money to feed, Musa is all by himself at home — somewhere in Oshodi — resigned to fate.
“In June 2017, I started experiencing excruciating pains in both legs; they legs swelled up, and at the end of the day, this one burst. You can see the opening,” he says, then gives in to a cough he had be trying hard to suppress.
“I went to Gbagada General Hospital,” he continues, “but they refused to attend to me. They said I should go back to LUTH, being my first clinic. When I got to LUTH, they said there was no available bed for me, and that they would take me to a private hospital: ₦50,000 deposit first, and ₦1million or more if I spent more than 10 days there. Even ₦5000 I didn’t have on me on that day, where was I supposed to get ₦50,000? from”
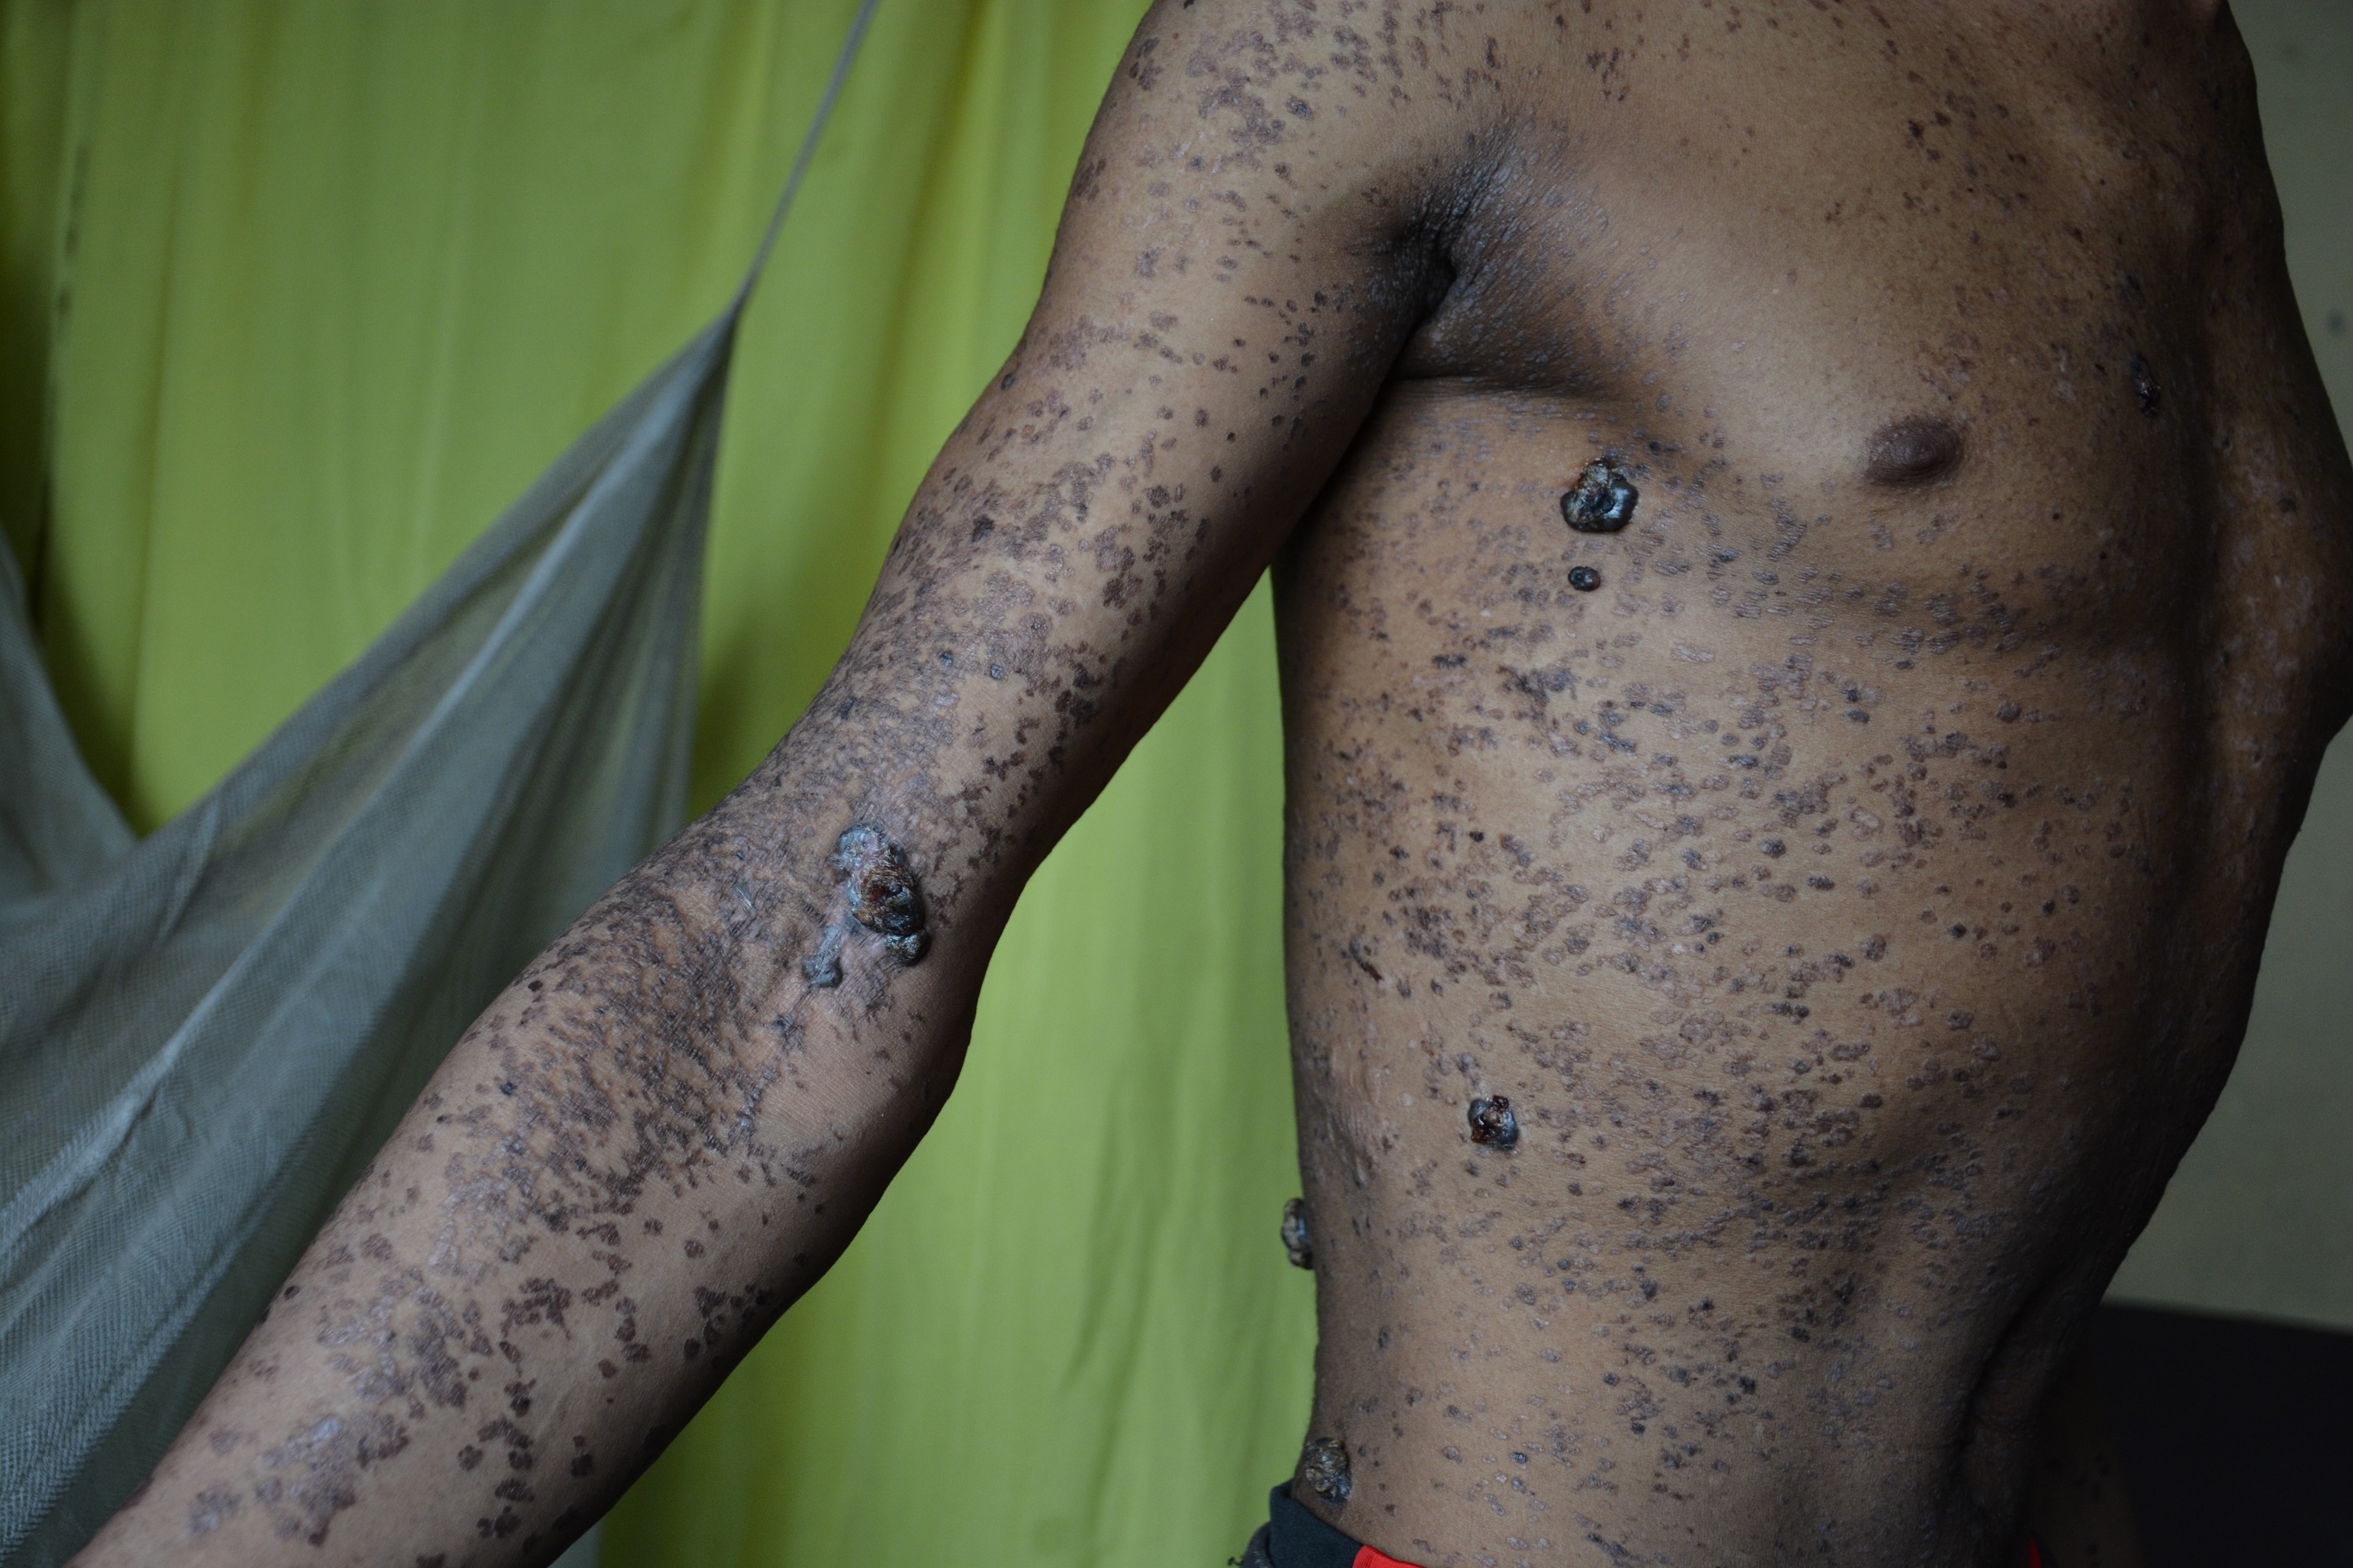
Musa’s problem is beyond the tumour overshadowing his right eye. To prove this, he removes his shirt and folds up his knickers, revealing spots of rashes and tumours marauding his skin. A thick stench at once rents the air at the penthouse from which the landlord is already threatening to eject him for defaulting on rent.
NO FOOD, NO WATER, FAILING HEALTH
More tumours are appearing on Musa’s body, and they’re growing fast!
“I’m sorry, my brother, but I have nothing to hide any longer. If I die today, the people who will bury me will get to see the nakedness I’m hiding. Look at me, I’m dying here but I don’t want to die. Please help me,” he says tearfully.
“I’ve run everywhere possible… no one to help. I wrote to the Ministry of Health; I wrote to the Lagos State government. They said they had no funds to assist me. My brother, I swear to God, since yesterday, even sachet water I have not seen to drink.”
Musa did get some help along the way, though. A house officer at LUTH picked interest in his case, and continued sending him money even at the expiration of his housemanship and relocation from Lagos to Ibadan. That doctor is now jobless, and as such, Musa is feeling the heat.
“It is only this doctor that has helped me when capable. But since he lost his job, I have been in a bad situation here. It is only if someone remembers me and decides to visit, maybe one of my mosque members, that I get something to eat.”
The bad news is that it looks his condition may get worse. He knows as much, admitting: “You know, these skin rashes have now started developing tumours; the doctors said they have stayed too long on my body. The only thing they can face is the tumour on my eyes. And when they’re done facing that one, we will be dealing with more tumours from those rashes.”
NO RADIOTHERAPHY IN LAGOS, NO BIOTHERAPY IN ZARIA
“Please help me, please help me,” a 64-year-old woman says in Pidgin English amid fits of cries and screams. “Doctor, abeg make una help me oooooooooo.”
Were the basic cancer treatment procedures in place, this woman would have no business with admission at LUTH’s gynecology ward. By the woman’s account, LUTH referred her to the Ahmadu Bello University Teaching Hospital (ABUTH), Zaria, to undergo biological therapy (biotherapy for short) — a type of treatment that uses substances made from living organisms to treat disease. Biotherapy is considered superior to chemotherapy because chemo drugs can’t differentiate between cancer cells and healthy cells in the body. As a result, chemotherapy causes damage to normal cells, which can result in nausea, fatigue, hair loss and other side effects associated with this type of treatment. Biotherapy, meanwhile, generally makes use of natural, living substances that bolster the immune system’s ability to fight cancer. In addition, some forms of biotherapy prevent specific cancer cells from growing, or even kill them. Compared to other cancer treatments, the side effects of biotherapy are notably low.
After listening to the woman, the undercover doctor explains what the LUTH doctors must have been thinking, in sending the woman to Zaria. “Sometimes, as a doctor, you assess some patients and you see clearly that there is a limit to the external gimmicks that you can make. So you complement with biotherapy.”
Worried by how her two children, both adolescents — one male, the other female — would survive should she die — the woman, a roadside roasted plantain seller at Ojo-Alaba, Lagos, borrowed money and endured a tumultuous road trip to Zaria from Lagos. Without enough money for hotel accommodation, she slept out in the cold during her few days in Zaria. That was in 2016. On arriving the teaching hospital in Zaria, she was told, first, that they were not expecting any patient from LUTH. The LUTH authorities hadn’t pre-contacted them. This could have been sorted out in a matter of days, but the bigger problem was that Zaria’s biotherapy machine had broken down.
“It’s not only Zaria; I know two teaching hospitals in Nigeria with the equipment to carry out biotherapy, but none of them as functioned in the past three years,” the undercover oncologist adds. “In fact, presently, there is no functional biotherapy equipment in any public hospital in Nigeria. Long and short, biotherapy is currently unavailable in Nigeria — and this is a function of equipment, not expertise.”
Ever since, the woman has been frequenting LUTH for drugs, tests and admission. But, on the evidence of current pains, the cancer in her cervix is spreading fast.
‘I DON’T WANT TO DIE… MY CHILDREN ARE STILL IN SCHOOL’
“Since then, I have been constantly complaining, especially regarding my stomach. It’s getting bigger and the pain is so much,” she says, again in tears. “I have spent a lot of money too, and on many scans that cost ₦40,000, ₦30,000 each. There is nothing, including scans and injections, they recommended that I have not done or bought, but my belly is swollen now and won’t return to normal size.”
The woman bursts into another round of please-help-me tears. The stomach aside, her left leg has swollen up. Various scans on the leg have yielded no solution. She is also one of the victims of the breakdown of LUTH’s radiotherapy machine; she had only completed a little more than half of the recommended radiotherapy sessions when the machine broke down in June 2016. Twice — with biotherapy and radiotherapy — this country has failed her. And this is after spending well over N1million on her health. Bear in mind that this is a roadside roasted plantain seller, and that the stomach and leg swellings and pains weren’t there pre-Zaria, when she first reported to LUTH.
“Please help me,” she sobs again, louder this time, as undercover oncologist and doctor make their way out of the ward. “Please, help me. It is the small money I make from my work that I use to send my children to school. I don’t want to run out of funds for their education. I don’t want to die while they’re still in school.”
A DAY AT LUTH’S ONCOLOGY AND RADIOTHERAPHY DEPARTMENT
LUTH’s oncology/radiotherapy department… early in the morning
On an average day, the Oncology Department at LUTH is like a tripartite arena. First part, early in the morning, it takes on the semblance of a graveyard. We’re talking 7:00, 7:30, 8:00am — cancer patients, old and young, male and female, are trickling in, some for confirmation of next laboratory tests, some for the highly-dreaded chemotherapy sessions, others for confirmation of surgery dates or for post-surgery evaluation.
The ward is generally quiet at this stage, save when the familiar faces of long-term patients interlock, paving the way for exchange of mild-witted niceties. Globally, cancer is a generally deadly disease. But Nigeria is where the death ratio is highest: 805 of 1,000 cases — or four in five cancer cases — result in death. According to statistics from the World Health Organisation (WHO), over 100,000 Nigerians are diagnosed with cancer annually, with 80,000 of them dying from the disease — an average of 240 Nigerians/day or 10 Nigerians/hour. As if that wasn’t enough, WHO has predicted that Nigeria can expect a 75 per cent increase in cancer-induced death by 2030. Add that to the chaotic and comatose health system and it can be said that in Nigeria, cancer is somewhat a death sentence, the reason the oncology ward usually wears a sombre, gloomy look early in the morning.
Usually, from a few minutes past 8am till 10am or thereabouts, a first-time visitor can be forgiven for thinking he missed his way and ended up in a church! This is the second part, comprising praise and worship, sermon and altar call. Then the third and final part is where the ward looks both like a hospital-cum-market: filling the attendance list, roll call of patients, loud complaints by angry patients.
When the journalist visited the department one Thursday in March, all three scenarios played out. First, the initial silence. But at 8:20am when a nurse comes in and tells the patients ‘Let us pray’, everything changes. After the prayer comes a praise and worship session that begins thus at exactly 8:55am: O se o Jesu/a o ma yin o/o se o Jesu/Olorun ayo wa (Thank you Jesus we will praise you, the source of our joy…). Soon, nurses and patients invite God to their midst to perform miracles, singing: Yahweh/Your name is Yahweh/You are the miracle working God/Your name is Yahweh, and later Come and do your miracle today/Your miracle today….
One look at the patients and one could tell they looked more to God for help than to the doctors at LUTH. And it is easy to see why: those of them scheduled for radiotherapy sessions understand that the doctors can do no magic if the government continues ignoring the hospital’s broken-down RT machine. In any case, the nurse leading the session soon touches the matter as praise and worship morphs into full-blown prayers. “Let us continue to pray for Nigeria and for our government,” she charges the patients. “It is our right to have this radiotherapy machine but unfortunately our government is not up to date in this wise. We are optimistic that things will improve very soon, but we must pray so this can happen quickly.”
The end of prayers at 9:22am isn’t it for the day, no. A female doctor — tall, fair and with a thick Igbo accent — takes over. It’s sermon time! It lasts approximately 20 minutes and is followed by the altar call: those who want to surrender their lives to Christ have the chance now. Of course, for a population of people afflicted by a disease that translates to a death sentence in their country, quite a number presented themselves. Who would blame them? Better to hand one’s live to Christ since Nigeria places no value on it, anyway. Altar call ends at exactly 9:49am; time, now, for the day’s main activities.
As the patients watch out for their names to have their moments with the doctor, there is a huge conversation about how the lack of a radiotherapy machine at LUTH was compounding their woes. By the accounts of five patients, private hospitals are taking advantage of the gap.
HELPING PATIENTS SEE DOCTORS IS LUCRATIVE BUSINESS
“I went to Eko Hospital after the breakdown of LUTH’s machine, and I was given a bill of N160,000,” says a slender, light-skinned woman. “But when I presented myself on appointment date, I was told that the cost had risen to N250,000. Apparently, Eko Hospital had become aware of the damage to LUTH’s machine, so they saw an opportunity to make quick money.”
“It’s blood money, I tell you!” another patient yells. “My own problem is that Eko Hospital is crowded these days; it’s so difficult to see the doctors.”
Having devised an underhand way around the challenge, the first patient offers some interesting advice: “There is this boy who lives not so far from the hospital; if you give him N500, he’ll go there around 2 or 3am to write your name on the patients’ list for the day. I can link you to him if you want, but that’s what I do.
“I started doing it since the day my husband and I spotted robbers around Jakande and Lawanson [on Victoria Island] when we left home around 4am because I needed to see the doctor early. We had to stop doing that; we won’t die before death comes.”
Were the boy to do that for 10 patients every day, that’s N5,000 daily — N25,000 at the end of the week.
Their conversation is interrupted by a woman who left her home in Ikorodu at 5am so she could arrive the hospital in time to see the doctor, but has now been told, at 11:06am, that her file is missing.
“What manner of nonsense is this?” the woman, dark, ostensibly in her mid-30s, says. “Can you imagine such utterance? As if I took my file home the last time!”
She returns to the hospital staff after 15 minutes but she is told to “stop disturbing us”. “This people are trying my patience,” she huffs. “I will leave them to their madness and go to my home, after all it is God who takes care of the sick.”
After about an hour of tussle, she is told to see the doctor; the file would be taken care of later.
File disappearances aren’t specific to LUTH. According to a doctor, who asked not to be named because of her close ties to the UCH, such disappearance once cost a patient’s life — indirectly.
“Few years back while working at UCH, I had this patient whom I suspected had breast cancer. But to be 100% sure, I sent her to the lab,” she recalls. “She did the test, but when the time came to collect it, UCH couldn’t find her result. She was told to pay a second time for another test.
“But this woman never came. Instead, her church members convinced her to focus on prayers. Guess what, she eventually died of cancer. If UCH hadn’t lost her test, she would have started treatment fairly early, and maybe she’d still be alive today.”
AT UCH, NO CONNECTION, NO RADIOTHERAPY
On his sick bed at the University College Hospital (UCH), this 54-year-old suffering from cancer of the anus cuts a frustrated figure. Since relocating to UCH in February (and this is March), he has taken in five pints of blood — in addition to seven at LUTH. And he has suffered. Each time he tries to talk, he finds that the strength left in him isn’t up to it. Then he resorts to tears. “I know I will get well,” he says intermittently, “and when I get well…”
His wife always cuts in: “Relax, honey; you will be fine.” She is his spokesman now. Not just that, his number-one caregiver, his manager, his comforter, his pillar. Another classic example of how listless life would be without love — how, without love, hospitals would be faster pathways to the graveyard.
“He was rejected at LASUTH because there was no bed space,” the undercover oncologist and journalist, who had found their way into UCH through the backdoor, overhear his wife say to a friend on the phone.
Even at LUTH, there was no bed space. But seeing how badly he needed to be admitted, the doctors took the difficult decision of searching round the ward to see who could be discharged. Finally, they found someone whose condition they thought was the least critical, and sent him home; but ordinarily, that patient would have remained on admission.
That admission at LUTH was short-lived, though. He needed radiotherapy and was told the machine would “soon” be repaired, but the wait was becoming endless. Earlier, he had also waited on the radiotherapy machine at the University of Nigeria Teaching Hospital (UNTH), Ituku-Ozalla, Enugu, for more than a month, but was eventually told it was “bad”. No longer willing to take risks, he decided to try UCH. But there was still one problem: it was January but UCH’s radiotherapy machine was already booked till April! Luckily, after his wife called a doctor-friend of hers, they received an expedited appointment. They arrived UCH in February, after more than three months of rejection by LASUTH and waiting on UCH and UNTH.
And so, while Eko Hospital is profiting from a lack of radiotherapy machine at LUTH, UCH is smarting from it. At UCH, there is increased competition for the machine to the extent that non-UCH patients have no chance of going under its radiotherapy machine early enough unless they’re connected to the hospital’s hierarchy.
On his sickness, they have spent more than N2million — more than half of that due to the endless wait for the machine. “We spent a lot of money on tests and drugs just to keep him in shape pending the readiness of the radiotherapy machine,” she says. “SO far, he’s had five radiotherapy sessions. Hopefully, he can get well soon.”
There are only four functioning radiotherapy machines all over the country to serve an estimated 200million Nigerians, yet the International Atomic Energy Agency (IAEA) recommendation is one RT machine per 1million people, meaning Nigeria should ordinarily have roughly 200 RT machines.
Of these four functioning machines in Nigeria, one is owned by Eko Hospital, a private hospital. This means that of the 20 federal teaching hospitals in the country, only three — UCH, Ahmadu Bello University Teaching Hospital Zaria and the National Hospital Abuja — currently have functional radiotherapy machines. The Usman Dan Fodio University Teaching Hospital Sokoto (under repairs), UNTH and LUTH have, but the machines have been down for varying long periods of time — that’s having like not having!
To put the situation in perspective, 17 of Nigeria’s 20 teaching hospitals cannot offer radiotherapy to cancer patients. Also, radiotherapy is unavailable in the entire South-South (comprising Akwa Ibom, Cross River, Bayelsa, Rivers, Delta and Edo states). Anyone diagnosed with cancer in this region must travel out of it — either to Enugu in the South-East, Lagos or Ibadan in the South-West, or Abuja in the North-Central. This trend is nothing new; there was a time in 2015 when only two radiotherapy machines were functioning in the whole country.
‘OLD SCHOOL’ RT MACHINES
A cobalt-60 RT machine purchased in 2017 by the Ugandan government
Painfully, of the four radiotherapy machines available all over Nigeria, only one — National Hospital Abuja’s — is useful for curing cancer; all other three cannot. They are only useful prolonging a patient’s life; more like ‘you’re going to die anyway but let’s try not to make you die too soon’.
So explains Runcie C. W. Chidiebe, a cancer control advocate and Executive Director, Project Pink Blue.
“The radiotherapy machines at Zaria and Eko hospital are cobalt machines,” Chidiebe moans.
“I have interacted with so many medical physicists, clinical oncologists and radiation oncologists, and they will tell you that the beam produced by cobalt radiotherapy machines is not sufficient to prevent spread or even ensure any treatment or therapy; it is just good for palliative care only — that is the situation whereby you’re no longer trying to achieve cure but just to prolong the patient’s life.”
Chidiebe was stunned to find out during a recent visit to Texas Oncology in Sherman, in US, that just one centre had two radiotherapy machines — one variam, the other linac accelerator — serving 100,000 people.
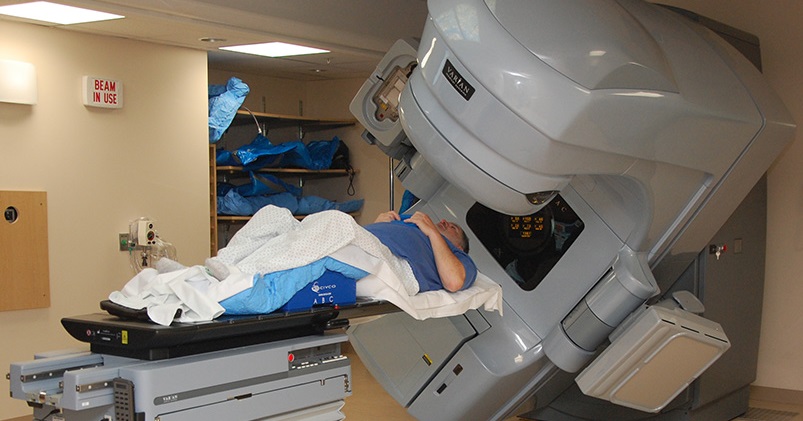
“None was cobalt!” he exclaims. “These are the newest machines that produce sufficient beams that can really contain the cancer and prevent it from spreading to other vital organs.”
THE RADIOTHERAPY HUSSLE IS REAL
A varian linac RT machine in use at the National Life Cancer Treatment Centre of the Central Vermont Medical Centre, US
An expected consequence of the scarcity of RT machine is the huge competition for sessions in the three hospitals where the service is available. In those hospitals, an appointment is extremely difficult to secure, and officials try their best not to offer guarantees on the stability of their RT machines.
“The machine is working,” a UCH official said on the phone when asked for how soon an appointment could be booked, before quickly adding emphatically: “as of today!”
A contact in the radiotherapy department was supplied, and, although the doctor at the other end hesitated to pin a date for a patient that hadn’t been physically examined, he eventually said: “If the patient comes and we discover that it is not an emergency, he cannot get a RT appointment before July.” That is four months of offering the cancer unfettered access to spread!
FINANCING FOR ONCOLOGY MUST IMPROVE
Chidiebe laments: No bone scan working in the entire country
So, what can be done to bolster the quality of treatment available to cancer patients, particularly in terms of access to RT?
“Most of the RT machines break down intermittently,” says Chidiebe. “Some don’t even work up to one month. It takes months to get money out for maintenance, but cancer doesn’t wait; it keeps spreading. We have refused every year to invest in cancer control. Financing for oncology and radiotherapy is so poor; it has to be improved.”
Another step, he explains, is for government to buy the machine spare parts and keep them, instead of waiting for the machines to develop fault.
“As I speak to you, there is no bone scan working across the country. We have two bone scan centres — UCH and National Hospital — but the problem is that there are no reagents,” he says.
“Can you imagine? The machines are there but no reagents. Isn’t it shameful? The nuclear medicine guys have to travel to South Africa to get these things. The Nigeria Customs Service are not helping issues, too, with the way they frustrate you with their corrupt demands when you try to bring these machine in.”
WHERE IS THE MONEY???
Adewole, Health Minister
The most expensive linac radiotherapy machines cost between of $750,000 and $1.5million (between N228 million and N456million, at the current CBN rate), excluding associated costs such as the vault that will house the system, treatment planning and oncology information system software, lasers, and other accessories.
However, only N55.6 billion was allocated to capital projects in the ministry of in the 2017 budget. In 2016, it was N28.7billion, N22.7billion in 2015, and N49.5billion in 2014. In 2017, a total of N4.01 billion was budgeted for all 20 teaching hospitals; it was N2.4billion in 2016, N1.8bn in 2015 and N9.3bn in 2014. That’s grossly inadequate, considering the enormous equipment deficiencies of those institutions, which perhaps explains why University of Port Harcourt Teaching Hospital, despite receiving the biggest share of the 2017 capital allocation (N492.8million), still doesn’t have a RT machine.
While the health sector is incontrovertibly underfunded, it would appear that the bigger problem is financial mismanagement, not under-funding. In the 2017 budget, N9 billion was specifically allotted to the purchase of radiotherapy machines for some teaching hospitals (and another N117 million was also budgeted for cancer-related issues).
Let’s make two unlikely assumptions: that the government purchases the most expensive linac RT machine in existence (N456million) and the associated costs are as expensive as the machine itself (another N456million). This would mean that at the very maximum, one RT machine would cost N912million. Therefore, the N9bn budget would have funded the purchase of nine radiotherapy machines.
But in 2017, the government bought only one RT machine — for the National Hospital! The question, then, is: where is the rest of the N8bn?
This was one of the many questions that would have been put forward to Isaac Adewole, a Professor of Gynaecology and Obstetrics and Minister of Health, and Osagie Ehanire, Minister of State for Health, but neither responded to the email and text message sent to them.
THE LONG-TERM SOLUTION
Universal Health Coverage (UHC) is the long-term solution, says Pink Oak’s Laz Eze
Dr. Laz Ude Eze, Executive Director of Pink Oak Cancer Trust — an NGO that raises funds to help cancer patients access better care — cannot understand why Nigeria can’t reproduce the success of even neighbouring African countries in making quality care available to cancer patients.
He recalls — and adds that “it is shameful” — that when all the radiotherapy machines in Nigeria broke down, Nigerians were travelling to Ghana for radiotherapy.
“These Ghanaian hospitals were not full-fledged government hospitals,” he says. “One was an initiative between the Swedish government and the Ghanaian government, bringing in some private investors. The hospitals where our presidents get treated abroad and all our public office holders run to with taxpayers’ money are not government hospitals. Most of them are private hospitals. So, why can’t we attract that level of investment here?”
The long-term solution to the cancer challenge, he is certain, is Universal Health Coverage (UHC), a mandatory health insurance for all Nigerians, enabling them to access the highest possible quality of healthcare without financial difficulty. He says the country’s decision-makers know this but the political will is lacking.
“That ‘without financial difficulty’ is a keyword. The health sector needs much more money than government currently allocates to it,” he says.
“With the UHC, everyone contributes to a medical fund. Everybody can’t get sick at the same time, therefore people with cancer can get treatment and don’t have to pay out of pocket; and if they have to, it will be something the person can afford.
“It doesn’t mean it has to be entirely free. But it has to be that no matter the level where the person operates, a patient will be able to afford healthcare. He doesn’t need to go bankrupt. You will not need to choose between feeding your family and paying for his health, or paying your child’s school fees and paying for your health. The opportunity cost will not need to be anything that is important to you. So it’s just like you want to buy coke — you know, that level — and you will not feel it. That’s the destination
“And it’s something that, if there’s political will to get it done, within two to three years, we can have it. We may say there is no money, but there is money for things that government considers important. If they don’t have money, they’d borrow to fund it. So, all the solution to this is for the government, at federal and state levels, to consider cancer as an important challenge.”
‘SOMEDAY IN THE FUTURE, WE’LL PAY FOR IT’
Would there be consequences if government continues ignoring the underwhelming quality of care available to cancer patients? Chidiebe says yes.
“It means people will continue to die unnecessarily, avoidably,” he says. “And you know the saddest thing? Most people who develop cancer are the aged whom we need to mentor the young ones. We’re raising a generation of youth lacking in mentoring by elders; and someday in the future, we will surely pay for it.”